You are here: Urology Textbook > Kidneys > Renal cell carcinoma > Surgical Treatment
Surgical Treatment for Renal Cell Carcinoma
- Renal cell carcinoma: Definition and Epidemiology
- Renal cell carcinoma: Pathology
- Renal cell carcinoma: Diagnostic workup
- Renal cell carcinoma: Surgical Treatment
- Renal cell carcinoma: Targeted therapy of advanced disease
Therapy
Overview of Treatment Options
Unilateral small kidney tumor:
Open partial nephrectomy, laparoscopic partial nephrectomy, or robot-assisted partial nephrectomy is the standard treatment, depending on the surgeon's technical expertise. Favorably located small tumors can be treated with radiofrequency ablation, microwave ablation, or cryotherapy. Active surveillance is an option for older patients with significant comorbidity.
Large unilateral kidney tumor:
Radical nephrectomy is the standard treatment for large tumors when partial nephrectomy is technically or oncologically unsuitable, and for tumors with extensive venous tumor thrombus. Favorably located large tumors may also be treated with partial nephrectomy. Depending on the disease stage and the surgeon's technical expertise, surgery may be performed laparoscopically, retroperitoneoscopically, with robot assistance, or by an open flank or transperitoneal approach.
Bilateral kidney tumors:
Partial nephrectomy should be attempted on both sides. If this does not appear technically feasible, partial nephrectomy is first performed on the technically simpler side. After recovery, residual renal function is evaluated by renal scintigraphy. If residual function on the operated side is sufficient, radical nephrectomy may be performed on the contralateral side. If residual function is inadequate, imperative partial nephrectomy of the contralateral kidney should be attempted using all available technical options; radical nephrectomy followed by dialysis is an alternative.
Metastatic renal cell carcinoma:
In metastatic disease, a multidisciplinary team should assess before treatment whether complete metastasectomy, local treatment of metastases, or cytoreductive nephrectomy is likely to provide meaningful benefit. Systemic therapy is generally the priority in patients with a high metastatic burden, poor performance status, or an unfavorable IMDC risk group (see the IMDC risk criteria). If surgery has removed all tumor manifestations, adjuvant pembrolizumab may be considered for clear cell histology. Metastases that cannot be removed surgically are treated systemically with combinations of immune checkpoint inhibitors and tyrosine kinase inhibitors or with immune checkpoint inhibitor combinations (see systemic therapy for metastatic renal cell carcinoma).
Radical Nephrectomy
Indication:
Radical nephrectomy is the standard treatment for large tumors or tumors with venous tumor thrombus.
Relative contraindications:
The availability of a suitable nephron-sparing partial nephrectomy for a small tumor is a relative contraindication to radical nephrectomy, particularly in patients with existing or impending renal insufficiency. Risk factors for future renal insufficiency after nephrectomy include elevated serum creatinine, proteinuria, diabetes mellitus, arterial hypertension, bilateral renal cell carcinoma, and familial renal cell carcinoma.
Surgical technique:
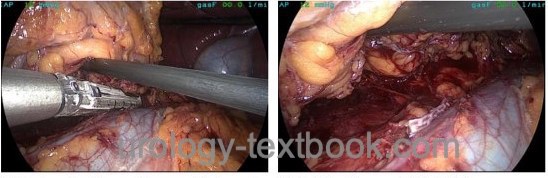
Radical nephrectomy may be performed laparoscopically, with robot assistance, or retroperitoneoscopically [for technique and complications, see radical nephrectomy]. Open flank, transperitoneal, or thoracoabdominal nephrectomy is an alternative, particularly for very large tumors. Minimally invasive nephrectomy has lower morbidity and is oncologically equivalent. No significant clinical differences have been demonstrated between the different approaches (EAU guideline).
 |
Venous invasion:
For tumors with venous thrombus, secure vascular control to open the inferior vena cava and complete removal of the tumor thrombus are prerequisites for nephrectomy. Accurate determination of the cranial extent of the thrombus is essential for surgical planning:
- Level I: Tumor thrombus in the renal vein
- Level II: Tumor thrombus in the inferior vena cava below the liver
- Level III: Tumor thrombus in the intrahepatic inferior vena cava below the diaphragm
- Level IV: Tumor thrombus extending above the diaphragm
Adrenalectomy:
If adrenal involvement is detected, the adrenal gland is removed during surgery for the primary tumor. Routine adrenalectomy without radiologic evidence of tumor involvement is generally not indicated.
Lymphadenectomy:
Lymphadenectomy should not be performed for cT1–2 cN0 tumors because a large EORTC study did not demonstrate a survival benefit (Blom et al., 2009). Based on retrospective data, some authors advocate an extended lymphadenectomy for advanced tumors or enlarged lymph nodes, extending from the diaphragmatic crura to the origin of the inferior mesenteric artery. For left-sided tumors, the para-aortic lymph nodes are removed; for right-sided tumors, the paracaval lymph nodes are removed. The interaortocaval lymph nodes should be removed regardless of tumor side.
Oncological results:
More precise estimates of survival can be obtained by considering multiple risk factors using the Stage, Size, Grade, and Necrosis (SSIGN) score [tables Assessing the SSIGN score and SSIGN score and survival].
| Risk factor | Score |
| T stage | |
| T1 | 0 |
| T2 | 1 |
| T3 | 2 |
| T4 | 4 |
| Lymph node status | |
| pNx/pN0 | 0 |
| pN1–2 | 2 |
| Metastases | |
| M0 | 0 |
| M1 | 4 |
| Tumor size | |
| < 5 cm | 0 |
| > 5 cm | 2 |
| Grade | |
| Grade 1–2 | 0 |
| Grade 3 | 1 |
| Grade 4 | 3 |
| Tumor necrosis | |
| Absent | 0 |
| Present | 2 |
| SSIGN score | 1 year | 5 years | 10 years |
| 0–2 | 99 % | 97 % | 94 % |
| 3–4 | 98 % | 90 % | 78 % |
| 5–6 | 93 % | 74 % | 57 % |
| 7–9 | 77 % | 39 % | 26 % |
| ≥10 | 43 % | 19 % | 19 % |
Adjuvant therapy:
The risk of recurrence is increased in locally advanced or node-positive renal cell carcinoma. Adjuvant systemic therapy is approved only for pembrolizumab in patients with clear cell histology and a high risk of recurrence; structured surveillance remains the standard outside this setting.
Adjuvant therapy with checkpoint inhibitors:
KEYNOTE-564 was the first phase III trial to demonstrate improved disease-free survival (HR 0.72) and improved overall survival (91 % vs. 86 % at four years) with adjuvant pembrolizumab after surgery (Choueiri et al., 2024). Included patients had dedifferentiated tumors (grade 4), T3–4 or N+ disease, or had undergone complete resection of metastases. The FDA approved treatment in November 2021 and the EMA in February 2022. Potential disadvantages of early adjuvant pembrolizumab include overtreatment of patients without metastatic disease, undertreatment of patients with metastatic disease who do not receive a tyrosine kinase inhibitor, and high costs.
Adjuvant therapy with tyrosine kinase inhibitors:
Several randomized studies examined adjuvant signal transduction inhibitors in patients at high risk of progression after surgery. ASSURE (sunitinib vs. sorafenib vs. placebo) showed no significant benefit. PROTECT (pazopanib vs. placebo) improved progression-free survival (HR 0.69), but did not demonstrate a difference in overall survival. S-TRAC (sunitinib vs. placebo) demonstrated improved progression-free survival but no established overall survival benefit. Long-term tyrosine kinase inhibitor therapy has significant adverse effects. Adjuvant therapy with these agents is not recommended outside controlled trials, and available signal transduction inhibitors are not approved for adjuvant treatment.
Follow-up after radical nephrectomy:
According to the EAU and German S3 guideline recommendations, follow-up after radical nephrectomy should be based on symptoms and the risk of metastasis. The risk can be estimated using the Stage, Size, Grade, and Necrosis (SSIGN) score [tables SSIGN score and SSIGN score and survival].
For patients at low risk, follow-up is recommended for five years. Clinical examinations, laboratory tests, and ultrasound examinations are recommended at months 3, 6, 12, 24, 36, 48, and 60. The EAU guideline recommends CT only if symptoms suggest recurrence. The German S3 guideline recommends CT of the chest and abdomen at years 1, 2, and 4.
For patients at intermediate or high risk, follow-up is recommended for nine years. Clinical examinations, laboratory tests, and ultrasound examinations are recommended at months 3, 6, 12, 24, 36, 48, 60, 84, and 108. CT of the chest and abdomen is recommended at years 1, 2, 3, 4, 5, 7, and 9. For patients at high risk, additional chest CT is recommended at months 6 and 18. Bone scintigraphy or whole-body low-dose CT is indicated for bone pain.
Local recurrence:
A local recurrence without evidence of distant metastases should be surgically removed whenever possible. After complete resection, the five-year survival rate is approximately 50 %.
Partial Nephrectomy
Imperative indications:
Partial nephrectomy is imperative when radical nephrectomy would result in renal insufficiency requiring dialysis. If oncologically feasible, partial nephrectomy is strongly indicated for:
- RCC in a solitary kidney
- Compensated renal insufficiency (chronic kidney disease)
- Bilateral tumors
- Familial renal cell carcinoma
- Known conditions that may lead to future renal insufficiency (e.g., diabetes mellitus or renal artery stenosis).
Elective indications:
The German S3 guideline clearly favors partial nephrectomy for localized renal cell carcinoma. If technically feasible, partial nephrectomy should be performed for T1 tumors and may be performed for T2 tumors instead of radical nephrectomy. Retrospective comparisons of radical and partial nephrectomy for T1 tumors found better survival after partial nephrectomy. This may be explained by a reduction in cardiovascular disease associated with better renal function. The randomized EORTC study did not demonstrate a survival benefit (van Poppel et al., 2011).
Surgical technique:
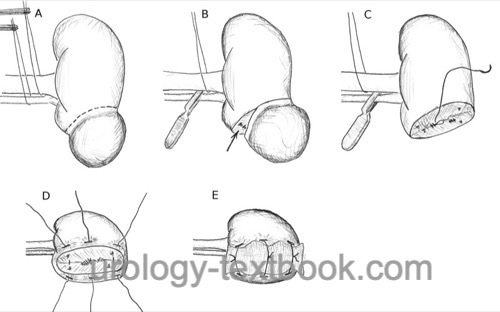
Open partial nephrectomy is performed through a flank or transperitoneal approach. Laparoscopic or robot-assisted partial nephrectomy can be performed transperitoneally or retroperitoneoscopically. After exposure and control of the renal hilar vessels, the tumor is excised with or without temporary ischemia, depending on tumor size, location, complexity, and bleeding risk. A wide safety margin is not required; a macroscopically tumor-free resection margin is essential. Enucleation along the pseudocapsule is oncologically acceptable for tumors with suitable morphology (Minervini et al., 2012). For technical details, see open partial nephrectomy.
 |
Comparative studies:
Compared with open surgery, minimally invasive procedures reduce postoperative pain, length of hospital stay, and morbidity related to the surgical approach. Compared with conventional laparoscopy, robot-assisted partial nephrectomy facilitates tumor dissection, reconstruction, and suturing, and enables complex partial nephrectomy for central or hilar tumors. Oncological outcomes are comparable with appropriate patient selection. Blood loss, complication rates, and warm ischemia time depend substantially on tumor complexity and surgeon experience (Xia et al., 2017).
Management of bilateral renal cell carcinoma:
The simpler partial nephrectomy is performed first to avoid dialysis due to transient ischemia of a solitary functioning kidney. After full recovery, residual renal function is assessed by renal scintigraphy. If it is sufficient, complex or central contralateral tumors may be treated with radical nephrectomy. If residual function is inadequate, imperative partial nephrectomy should be attempted if technically feasible.
Oncological results:
The randomized EORTC study of 541 patients confirmed the oncological safety of partial nephrectomy for small resectable renal tumors (van Poppel et al., 2011). Tumor progression and cancer-specific mortality were rare in both study arms; a significant overall survival benefit from partial nephrectomy was not demonstrated. Prognosis after partial nephrectomy is determined primarily by tumor stage, tumor size, grade, histologic subtype, and distant metastases (see tables SSIGN score and SSIGN score and survival). Local recurrence is uncommon but is more likely with higher tumor stage, unfavorable tumor biology, and positive surgical margins.
Significance of positive surgical margins:
According to the German S3 guideline, partial nephrectomy may be performed without frozen-section examination if complete macroscopic tumor removal is achieved intraoperatively. Microscopic positive surgical margins primarily increase the risk of local recurrence; their effects on metastatic risk and overall survival are smaller. Prophylactic completion nephrectomy is not recommended for a microscopic R1 resection without imaging evidence of residual tumor. Instead, intensified risk-adapted follow-up is indicated; further local treatment or nephrectomy is performed if local recurrence is confirmed (German S3 guideline).
Follow-up after partial nephrectomy:
After a close-margin or R1 resection, abdominal CT three months after surgery is useful as a baseline for postoperative changes. Follow-up after partial nephrectomy should be based on symptoms and the risk of metastasis. Risk can be estimated using the Stage, Size, Grade, and Necrosis (SSIGN) score [tables SSIGN score and SSIGN score and survival]; see also follow-up recommendations after radical nephrectomy.
Alternative Treatment Options for Localized Small Renal Tumors
Options include active surveillance and thermal ablation, such as cryotherapy, radiofrequency ablation, or microwave ablation. The German S3 guideline recommends tumor biopsy before invasive ablation. Complication rates for ablative procedures are low to moderate and depend substantially on tumor size, location, and technique. Comparative long-term data are unavailable.
Cryotherapy:
Cryotherapy is delivered percutaneously or laparoscopically. Rapid tissue cooling, gradual thawing, and repeated freeze-thaw cycles are essential for cell destruction. The frozen tissue is resorbed and replaced by granulation tissue. Laparoscopic cryotherapy offers several advantages: the mobilized kidney can be cooled more effectively, the risk of injury to adjacent organs is minimized, and the ice ball can be visualized in relation to the tumor margins.
Radiofrequency and microwave ablation:
Peripheral small tumors can be treated with radiofrequency or microwave ablation. Compared with cryotherapy, monitoring the treatment effect is more difficult.
Active surveillance for T1a renal cell carcinoma:
Active surveillance is an option for small renal tumors in older patients with significant comorbidity. For tumors smaller than 3–4 cm, 22–46 % of renal tumors are benign. Among renal cell carcinomas, fewer than 10 % are poorly differentiated [table Renal tumor pathology by tumor size]. Active surveillance should be reconsidered if the primary tumor grows significantly or exceeds 3–4 cm.
| RCC diagnosis | Index | RCC metastasis therapy |
Index: 1–9 A B C D E F G H I J K L M N O P Q R S T U V W X Y Z
References
Blom u.a. 1999 BLOM, J. H. ; POPPEL, H. van ;
MARECHAL, J. M. ; JACQMIN, D. ; SYLVESTER, R. ;
SCHRODER, F. H. ; PRIJCK, L. de:
Radical nephrectomy with and without lymph node dissection:
preliminary results of the EORTC randomized phase III protocol 30881. EORTC
Genitourinary Group.
In: Eur Urol
36 (1999), Nr. 6, S. 570–5
Blom, Jan H M; van Poppel, Hein; Maréchal, Jean M;
Jacqmin, Didier; Schröder, Fritz H; de Prijck, Linda; Sylvester, Richard &
E. O. R. T. C. Genitourinary Tract Cancer Group
Radical nephrectomy
with and without lymph-node dissection: final results of European
Organization for Research and Treatment of Cancer (EORTC) randomized phase
3 trial 30881.
Eur Urol, 2009, 55, 28-34.
Capitanio, U.; Becker, F.; Blute, M. L.; Mulders, P.;
Patard, J.; Russo, P.; Studer, U. E. & Poppel, H. V.
Lymph node
dissection in renal cell carcinoma.
Eur Urol, 2011,
60, 1212-1220.
Choueiri TK, Tomczak P, et al., KEYNOTE-564 Investigators. Overall Survival with Adjuvant Pembrolizumab in Renal-Cell Carcinoma. N Engl J Med. 2024 Apr 18;390(15):1359-1371. doi: 10.1056/NEJMoa2312695.
DGU; DKG; DKG & Leitlinienprogramm Onkologie Diagnostik, Therapie und Nachsorge des Nierenzellkarzinoms, Langversion 4.02023 https://www.leitlinienprogramm-onkologie.de/leitlinien/nierenzellkarzinom/.
Gill, I. S.; Matin, S. F.; Desai, M. M.; Kaouk, J. H.;
Steinberg, A.; Mascha, E.; Thornton, J.; Sherief, M. H.; Strzempkowski, B.
& Novick, A. C.
Comparative analysis of laparoscopic versus open
partial nephrectomy for renal tumors in 200 patients.
J Urol, 2003,
170, 64-68.
Guinan u.a. 1995 GUINAN, P. D. ; VOGELZANG,
N. J. ; FREMGEN, A. M. ; CHMIEL, J. S. ;
SYLVESTER, J. L. ; SENER, S. F. ; IMPERATO, J. P.:
Renal cell carcinoma: tumor size, stage and survival. Members of the
Cancer Incidence and End Results Committee.
In: J Urol
153 (1995), Nr. 3 Pt 2, S. 901–3
Han u.a. 2003 HAN, K. R. ; BUI, M. H. ;
PANTUCK, A. J. ; FREITAS, D. G. ; LEIBOVICH,
B. C. ; DOREY, F. J. ; ZISMAN, A. ; JANZEN,
N. K. ; MUKOUYAMA, H. ; FIGLIN, R. A. ;
BELLDEGRUN, A. S.:
TNM T3a renal cell carcinoma: adrenal gland involvement is not the
same as renal fat invasion.
In: J Urol
169 (2003), Nr. 3, S. 899–903; discussion 903–4
A. K. Hemal, A. Kumar, R. Kumar, P. Wadhwa, A. Seth, und N. P. Gupta.
Laparoscopic versus open radical nephrectomy for large renal tumors:
a long-term prospective comparison.
J Urol, 177 (3): 862–866, Mar 2007.
Jocham u.a. 2004 JOCHAM, D. ; RICHTER, A. ;
HOFFMANN, L. ; IWIG, K. ; FAHLENKAMP, D. ;
ZAKRZEWSKI, G. ; SCHMITT, E. ; DANNENBERG, T. ;
LEHMACHER, W. ; WIETERSHEIM, J. von ; DOEHN, C.:
Adjuvant autologous renal tumor cell vaccine and risk of tumour
progression in patients with renal-cell carcinoma after radical nephrectomy:
phase III, randomised controlled trial.
In: Lancet
363 (2004), Nr. 9409, S. 594–9
B. Ljungberg et al., “EAU Guidelines: Renal Cell Carcinoma.” (2024). https://uroweb.org/guidelines/renal-cell-carcinoma/
Margulis, V.; Master, V. A.; Cost, N. G.; Leibovich, B.
C.; Joniau, S.; Kuczyk, M.; Mulders, P. F.; Kirkali, Z.; Wirth, M. P.;
Hirao, Y.; Rawal, S.; Chong, T. W. & Wood, C. G.
International
consultation on urologic diseases and the European association of urology
international consultation on locally advanced renal cell carcinoma.
Eur
Urol, 2011, 60, 673-683.
Minervini, A.; Serni, S.; Tuccio, A.; Siena, G.;
Vittori, G.; Masieri, L.; Giancane, S.; Lanciotti, M.; Khorrami, S.;
Lapini, A. & Carini, M.
Simple enucleation versus radical
nephrectomy in the treatment of pT1a and pT1b renal cell carcinoma.
Ann
Surg Oncol, 2012, 19, 694-700.
Poppel, H. V.; Pozzo, L. D.; Albrecht, W.; Matveev, V.;
Bono, A.; Borkowski, A.; Colombel, M.; Klotz, L.; Skinner, E.; Keane, T.;
Marreaud, S.; Collette, S. & Sylvester, R.
A prospective,
randomised EORTC intergroup phase 3 study comparing the oncologic outcome
of elective nephron-sparing surgery and radical nephrectomy for low-stage
renal cell carcinoma.
Eur Urol, 2011, 59, 543-552.
Robson u.a. 2002 ROBSON, C. J. ; CHURCHILL,
B. M. ; ANDERSON, W.:
The results of radical nephrectomy for renal cell carcinoma. 1969.
In: J Urol
167 (2002), Nr. 2 Pt 2, S. 873–5; discussion 876–7
Sun, M.; Trinh, Q.; Bianchi, M.; Hansen, J.; Hanna, N.;
Abdollah, F.; Shariat, S. F.; Briganti, A.; Montorsi, F.; Perrotte, P. &
Karakiewicz, P. I.
A non-cancer-related survival benefit is associated
with partial nephrectomy.
Eur Urol, 2012, 61,
725-731.
Tsui u.a. 2000 TSUI, K. H. ; SHVARTS, O. ;
SMITH, R. B. ; FIGLIN, R. A. ; DEKERNION, J. B. ;
BELLDEGRUN, A.:
Prognostic indicators for renal cell carcinoma: a multivariate
analysis of 643 patients using the revised 1997 TNM staging criteria.
In: J Urol
163 (2000), Nr. 4, S. 1090–5; quiz 1295
Weight, C. J.; Larson, B. T.; Fergany, A. F.; Gao, T.; Lane, B. R.; Campbell, S. C.; Kaouk, J. H.; Klein, E. A. & Novick, A. C.
Nephrectomy induced chronic renal insufficiency is associated with increased risk of
cardiovascular death and death from any cause in patients with localized
cT1b renal masses.
J Urol, 2010, 183, 1317-1323
Xia L, Wang X, Xu T, Guzzo TJ. Systematic Review and Meta-Analysis of Comparative Studies Reporting Perioperative Outcomes of Robot-Assisted Partial Nephrectomy Versus Open Partial Nephrectomy. J Endourol. 2017 Sep;31(9):893-909. doi: 10.1089/end.2016.0351.
Zini, L.; Perrotte, P.; Capitanio, U.; Jeldres, C.; Shariat, S. F.; Antebi, E.; Saad, F.; Patard, J.; Montorsi, F. &
Karakiewicz, P. I.
Radical versus partial nephrectomy: effect on
overall and noncancer mortality.
Cancer, 2009, 115,
1465-1471
 Deutsche Version: Nierenzellkarzinom
Urology-Textbook.com – Choose the Ad-Free, Professional Resource
This website is designed for physicians and medical professionals. It presents diseases of the genital organs through detailed text and images. Some content may not be suitable for children or sensitive readers. Many illustrations are available exclusively to Steady members. Are you a physician and interested in supporting this project? Join Steady to unlock full access to all images and enjoy an ad-free experience. Try it free for 7 days—no obligation.
New release: The first edition of the Urology Textbook as an e-book—ideal for offline reading and quick reference. With over 1300 pages and hundreds of illustrations, it’s the perfect companion for residents and medical students. After your 7-day trial has ended, you will receive a download link for your exclusive e-book.