You are here: Urology Textbook > Kidneys > Renal cell carcinoma > Treatment of advanced renal cell carcinoma
Treatment of Metastatic Renal Cell Carcinoma
- Renal cell carcinoma: Definition and Epidemiology
- Renal cell carcinoma: Pathology
- Renal cell carcinoma: Diagnostic workup
- Renal cell carcinoma: Surgical Treatment
- Renal cell carcinoma: Targeted therapy of Metastases
Prognosis and risk assessment
Criteria for assessing prognosis in metastatic renal cell carcinoma were developed in randomized trials. The Motzer score from the MSKCC was historically widely used (Motzer et al., 2002); it is based on studies from the cytokine era (see table Motzer criteria). The IMDC score is now more commonly used for treatment planning and incorporates patient data from studies of VEGF-targeted therapy (Heng et al., 2013). See table IMDC score for the criteria and survival of the risk groups.
| Risk factor | Threshold |
|---|---|
| Reduced Karnofsky index | < 80 % |
| Elevated LDH | > 1.5 times the upper limit of normal |
| Low hemoglobin | Below the lower limit of normal |
| Elevated corrected calcium | > 10 mg/dl or 2.4 mmol/l |
| Time from diagnosis to systemic therapy | < 1 year |
| Risk factor | Threshold |
|---|---|
| Reduced Karnofsky index | < 80 % |
| Elevated neutrophils | > upper limit of normal |
| Elevated platelets | > upper limit of normal |
| Low hemoglobin | Below the lower limit of normal |
| Elevated corrected calcium | > 10 mg/dl or 2.4 mmol/l |
| Time from diagnosis to systemic therapy | < 1 year |
Surgical therapy of the primary tumor and metastases
If complete resection of all metastases and the primary tumor is possible, surgery without neoadjuvant systemic therapy may be appropriate. Depending on the site of the metastases (lung, liver, or bone), the relevant surgical specialties should be consulted. Despite complete resection of all visible lesions, the risk of recurrence remains high. Surgery may delay the need for drug therapy and probably improve patient prognosis. Other benefits of metastasectomy include palliation of local symptoms.
The prognosis after resection of a solitary metastasis is less favorable if the metastasis was present at initial diagnosis. If the metastasis is detected during tumor surveillance, the interval between initial diagnosis and development of metastasis is prognostically important.
Cytoreductive nephrectomy
Cytoreductive nephrectomy is removal of the primary tumor in synchronous metastatic renal cell carcinoma. It is palliative, and systemic therapy remains necessary. In the cytokine era, nephrectomy before interferon-based immunotherapy improved survival in selected patients (Mickisch et al., 2001). These results cannot be directly extrapolated to current combinations of immune checkpoint inhibitors.
Two randomized trials, CARMENA and SURTIME, evaluated cytoreductive nephrectomy before treatment with inhibitors of signal transduction. Neither demonstrated a benefit from nephrectomy before sunitinib (Méjean et al., 2018) (Bex et al., 2019); however, both trials included only patients with intermediate- or poor-risk disease.
The role of cytoreductive nephrectomy in the era of immune checkpoint inhibitor combinations has not been definitively established in randomized trials. Initial systemic therapy is recommended for patients with poor-risk disease, poor performance status, high metastatic burden, or rapid tumor progression. Delayed cytoreductive nephrectomy may be reconsidered if the disease responds to or remains stable with systemic therapy. Immediate cytoreductive nephrectomy is an option only for patients in good general condition who have a low metastatic burden and a large or symptomatic primary tumor.
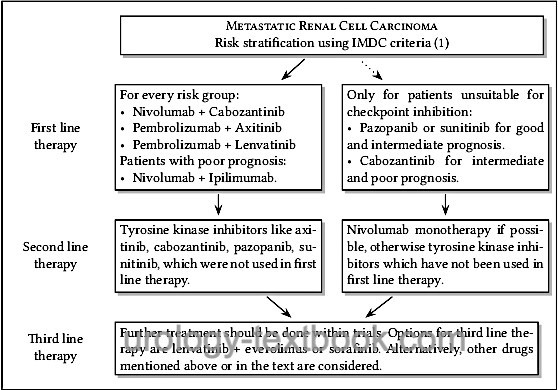
(1) Assess prognosis using table IMDC score.
Immune checkpoint inhibitors
Activation of immune checkpoint receptors suppresses the cellular immune response. These receptors normally prevent excessive immune responses and autoimmunity. Several receptors have been identified, including PD-1 (programmed cell death protein 1) and CTLA-4 (cytotoxic T-lymphocyte-associated protein 4) on T lymphocytes, and their ligands, such as PD-L1. Tumors use these pathways to induce immune tolerance. See section checkpoint inhibitor pharmacology and side effects on p. the relevant section for the pharmacology and side effects of checkpoint inhibitors (CPIs).
Several trials have demonstrated the superiority of combination first-line therapies over sunitinib. Established options include pembrolizumab/axitinib, pembrolizumab/lenvatinib, and nivolumab/cabozantinib across IMDC risk groups, as well as nivolumab/ipilimumab, particularly for intermediate- or poor-risk disease. These treatments produce complete remission in up to 10 % of patients and often result in a substantial response, although the response may be delayed. Side effects are substantial and differ between ICI/ICI and ICI/TKI combinations. A switch to the next treatment option is indicated only for clear progression or intolerable side effects (see fig. sequential therapy of metastatic renal cell carcinoma).
First-line therapy with nivolumab and cabozantinib
In the CheckMate-9ER trial, this combination improved progression-free survival (56 % vs. 27 %), complete response (14 % vs. 5 %), and overall survival (47 vs. 37 months) compared with sunitinib across all risk groups (Motzer et al., 2025).
First-line therapy with nivolumab and ipilimumab
In the CheckMate-214 trial, this combination improved progression-free and overall survival compared with sunitinib in patients with intermediate- or poor-risk disease (56 vs. 38 months after five years of follow-up). The combination also produces good responses in sarcomatoid renal cell carcinoma (Albiges et al., 2020).
First-line therapy with pembrolizumab and axitinib
In the KEYNOTE-426 trial, this combination improved progression-free survival and overall survival compared with sunitinib (HR 0.59; 1-year survival rate 90 % vs. 79 %) (Rini et al., 2019). The benefit was independent of IMDC risk group and PD-L1 expression.
First-line therapy with pembrolizumab and lenvatinib
This combination improved progression-free survival (24 vs. 9 months) and overall survival (HR 0.66) compared with sunitinib in the CLEAR trial (Motzer et al., 2021).
Second-line therapy with nivolumab
After TKI failure, nivolumab improved progression-free survival, response rate (CR + PR: 25 % vs. 5 %), and overall survival (25 vs. 20 months) compared with everolimus, with fewer side effects (Motzer et al., 2015).
Targeted therapy with inhibitors of signal transduction
Treatment with inhibitors of signal transduction (“ targeted therapy”) replaced immunotherapy with interferon or interleukin and became the standard of care before immune checkpoint inhibition was established. Tyrosine kinase inhibitors (TKIs) are currently administered in combination with immune checkpoint inhibitors (see above), or as monotherapy when CPIs are contraindicated. Inhibitors of signal transduction usually produce stable disease; complete remission is rare. Favorable signs of response include metastases that decrease in size or remain stable and show reduced perfusion compared with baseline.
The side effect profile of TKI monotherapy is more favorable than that of immunotherapy or combination therapy with immune checkpoint inhibitors (see above). Sequential therapy is recommended, with each agent continued for as long as possible. A switch to the next agent is indicated only in the event of clear progression or intolerable side effects despite treatment and dose reduction (see fig. sequential therapy of metastatic renal cell carcinoma). For TKI dosage, pharmacology, and side effects, see the Axitinib pharmacology section
Axitinib
Axitinib is an oral VEGF receptor tyrosine kinase inhibitor. It is approved for the following indications:
- First-line therapy in combination with pembrolizumab or avelumab for advanced renal cell carcinoma; see above.
- Second-line therapy if it was not used in the first line.
Cabozantinib
Cabozantinib is an oral tyrosine kinase inhibitor of targets including MET, VEGFR, and AXL. It is approved for the following indications:
- First-line therapy in combination with nivolumab; see above.
- First-line monotherapy for patients with intermediate- or poor-risk disease who have contraindications to checkpoint inhibitors. In the CABOSUN trial, cabozantinib prolonged progression-free survival compared with sunitinib (9 vs. 5 months) (Choueiri et al., 2018).
- Second- or third-line therapy for metastatic renal cell carcinoma if cabozantinib has not previously been used. In the METEOR trial, cabozantinib prolonged progression-free and overall survival compared with everolimus (Choueiri et al., 2015).
mTOR inhibitors
Everolimus and temsirolimus are inhibitors of mTOR (mechanistic target of rapamycin), a central regulator of cell growth, angiogenesis, energy metabolism, and apoptosis (Faivre et al., 2006). Everolimus was used as monotherapy after progression on VEGF-targeted therapy (Motzer et al., 2008), but now has only a limited role as monotherapy. The combination of lenvatinib and everolimus is more clinically relevant as subsequent therapy (see below). Temsirolimus was used as first-line therapy for tumors with a poor prognosis and now has only a limited role in third-line therapy.
Lenvatinib
Lenvatinib is a multikinase inhibitor of VEGF receptor kinases, FGFR kinases, PDGF receptor kinases, and c-KIT. It is approved for the following indications:
- First-line therapy in combination with pembrolizumab; see above.
- Second-line therapy in combination with everolimus. In patients whose disease has progressed after antiangiogenic therapy, the combination prolonged progression-free and overall survival compared with everolimus monotherapy (26 vs. 15 months for overall survival) (Motzer et al., 2015a). The combination is also a relevant later-line option after prior immune checkpoint inhibitor-based therapy.
Pazopanib
Pazopanib is an oral multikinase inhibitor of VEGF receptors, PDGF receptors, and KIT. It is an option for first-line therapy in patients with a favorable or intermediate prognosis who have contraindications to checkpoint inhibitors. It may be considered in later lines if it has not previously been used.
Sorafenib
Sorafenib is an oral multikinase inhibitor that acts on intracellular signaling pathways involved in cell growth and angiogenesis. Its targets include RAF kinase, VEGF receptor kinases, PDGF receptor kinase, KIT, and FLT-3. Sorafenib is a treatment option after first- and second-line therapy has failed.
Sunitinib
Sunitinib is an oral multikinase inhibitor, particularly of tyrosine kinases such as VEGF and PDGF receptor kinases. It is an option for first-line therapy in patients with a favorable or intermediate prognosis who have contraindications to checkpoint inhibitors. It may be considered in later lines if it has not previously been used.
Belzutifan
Belzutifan is a well-tolerated inhibitor of hypoxia-inducible factor 2α (HIF-2α). It is approved for the treatment of VHL-associated tumors (Jonasch et al., 2021) and for third-line therapy after a checkpoint inhibitor and a TKI. In the LITESPARK-005 trial, belzutifan improved progression-free survival compared with everolimus (34 % vs. 18 %); the difference in overall survival was not significant (Choueiri et al., 2024). Several phase 3 trials are investigating belzutifan as first-line therapy for metastatic clear cell renal cell carcinoma.
Immunotherapy with interferon and interleukin
Treatment with interferon-α in combination with interleukin-2 and 5-FU was an option for metastatic renal cell carcinoma. Interferon and interleukin are no longer used since inhibitors of signal transduction and immune checkpoints became available.
Chemotherapy for metastatic renal cell carcinoma
The following regimens have been tested with only moderate activity: gemcitabine and 5-FU, and gemcitabine combined with immunotherapy. No regimen has become established in clinical practice.
Palliative therapy for metastatic renal cell carcinoma
Painful bone metastases
Optimize pain management. Additional treatment options include radiation therapy, bisphosphonates (zoledronate), denosumab, and surgical stabilization.
Hypercalcemia
Treatment options include high-dose corticosteroids, forced diuresis, saline infusion, and bisphosphonates.
Local tumor pain or bleeding
Palliative nephrectomy or embolization.
Brain metastases
Corticosteroids and, depending on the extent of disease, stereotactic radiation therapy or whole-brain radiation therapy.
Prognosis
Growth of the primary tumor
Renal tumors grow by an average of 3–5 mm per year; some smaller tumors grow considerably more slowly. Metastasis from tumors less than 3 cm in diameter is rare.
Localized tumor stage
More precise estimates of survival are possible by considering several risk factors, including the stage, size, grade, and necrosis (SSIGN) score [tables SSIGN score and SSIGN survival data].
Venous invasion
Nearly 40 % of patients with venous invasion are pN0 and M0. Twenty-six percent have lymph node metastases, and 54 % have distant metastases.
Grading
Five-year survival rates by grade are G1 (89 %), G2 (65 %), and G3 (46 %).
Systemic metastases
Metastatic renal cell carcinoma has a poor prognosis, but is increasingly treatable. Patients with metastases at initial diagnosis have a worse prognosis than those who develop metachronous metastases later. The interval from initial diagnosis to the development of metastases is prognostically important because it reflects the rate of progression of systemic disease. Compared with liver, bone, or brain metastases, pulmonary metastases are associated with a more favorable prognosis. In addition to metastases at other sites, the following factors indicate a poor prognosis: low Karnofsky index, anemia, elevated corrected serum calcium, elevated LDH, elevated alkaline phosphatase, elevated platelet count, and elevated neutrophil count. See the IMDC score [table IMDC score] for mean survival under modern systemic therapy.
| RCC surgical therapy | Index | Wilms-Tumor |
Index: 1–9 A B C D E F G H I J K L M N O P Q R S T U V W X Y Z
References
L. Albiges, N. M. Tannir, M. Burotto, D. McDermott, E. R. Plimack, and R. J. Motzer, “Nivolumab plus ipilimumab versus sunitinib for first-line treatment of advanced renal cell carcinoma: extended 4-year follow-up of the phase III CheckMate 214 trial.,” ESMO open, vol. 5, no. 6, p. e001079, 2020.
Choueiri, T. K.; Escudier, B.; Powles, T.; Mainwaring,
P. N.; Rini, B. I.; Donskov, F.; Hammers, H.; Hutson, T. E.; Lee, J.-L.;
Peltola, K.; Roth, B. J.; Bjarnason, G. A.; Géczi, L.; Keam, B.; Maroto,
P.; Heng, D. Y. C.; Schmidinger, M.; Kantoff, P. W.; Borgman-Hagey, A.;
Hessel, C.; Scheffold, C.; Schwab, G. M.; Tannir, N. M.; Motzer, R. J. & ,
M. E. T. E. O. R. I.
Cabozantinib versus Everolimus in Advanced
Renal-Cell Carcinoma.
N Engl J Med, 2015, 373,
1814-1823.
T. K. Choueiri et al., “Cabozantinib versus sunitinib as initial therapy for metastatic renal cell carcinoma of intermediate or poor risk (Alliance A031203 CABOSUN randomised trial): Progression-free survival by independent review and overall survival update.,” Eur J Cancer, vol. 94, pp. 115–125, 2018, doi: 10.1016/j.ejca.2018.02.012.
T. K. Choueiri et al., “Belzutifan versus Everolimus for Advanced Renal-Cell Carcinoma.,” NEJM, vol. 391, no. 8, pp. 710–721, 2024.
DGU; DKG; DKG & Leitlinienprogramm Onkologie Diagnostik, Therapie und Nachsorge des Nierenzellkarzinoms, Langversion 4.02023 https://www.leitlinienprogramm-onkologie.de/leitlinien/nierenzellkarzinom/.
Escudier u.a. 2007 ESCUDIER, Bernard ; EISEN,
Tim ; STADLER, Walter M. ; SZCZYLIK, Cezary ;
OUDARD, Stéphane ; SIEBELS, Michael ; NEGRIER,
Sylvie ; CHEVREAU, Christine ; SOLSKA, Ewa ;
DESAI, Apurva A. ; ROLLAND, Frédéric ; DEMKOW,
Tomasz ; HUTSON, Thomas E. ; GORE, Martin ;
FREEMAN, Scott ; SCHWARTZ, Brian ; SHAN, Minghua ;
SIMANTOV, Ronit ; BUKOWSKI, Ronald M. ; GROUP, T.
A. R. G. E. T. S.:
Sorafenib in advanced clear-cell renal-cell carcinoma.
In: N Engl J Med
356 (2007), Jan, Nr. 2, S. 125–134
B. Escudier, T. K. Choueiri, S. Oudard, C. Szczylik, S. Negrier, A. Ravaud,
C. Chevreau, P. Venner, P. Champagne, D. Croteau, E. Dupont, C. Hariton, and
R. M. Bukowski.
Prognostic factors of metastatic renal cell carcinoma after failure
of immunotherapy: new paradigm from a large phase iii trial with shark
cartilage extract ae 941.
J Urol, 178 (5): 1901–1905, Nov 2007.
doi: rm10.1016/j.juro.2007.07.035.
URL https://dx.doi.org/10.1016/j.juro.2007.07.035.
B. Escudier, A. Pluzanska, P. Koralewski, A. Ravaud, S. Bracarda, C. Szczylik,
C. Chevreau, M. Filipek, B. Melichar, E. Bajetta, V. Gorbunova, J. O. Bay,
I. Bodrogi, A. Jagiello-Gruszfeld, und N. Moore.
Bevacizumab plus interferon alfa-2a for treatment of metastatic renal
cell carcinoma: a randomised, double-blind phase iii trial.
Lancet, 370 (9605): 2103–2111, Dec 2007.
S. Faivre, G. Kroemer, and E. Raymond.
Current development of mtor inhibitors as anticancer agents.
Nat Rev Drug Discov, 5 (8): 671–688, Aug
2006.
doi: rm10.1038/nrd2062.
URL https://dx.doi.org/10.1038/nrd2062.
Frank u.a. 2003 FRANK, I. ; BLUTE, M. L. ;
CHEVILLE, J. C. ; LOHSE, C. M. ; WEAVER, A. L. ;
LEIBOVICH, B. C. ; ZINCKE, H.:
A multifactorial postoperative surveillance model for patients with
surgically treated clear cell renal cell carcinoma.
In: J Urol
170 (2003), Nr. 6 Pt 1, S. 2225–32
Gold u.a. 1996 GOLD, P. J. ; FEFER, A. ;
THOMPSON, J. A.:
Paraneoplastic manifestations of renal cell carcinoma.
In: Semin Urol Oncol
14 (1996), Nr. 4, S. 216–22
Heng, D. Y. C.; Wells, J. C.; Rini, B. I.; Beuselinck,
B.; Lee, J.-L.; Knox, J. J.; Bjarnason, G. A.; Pal, S. K.;
Kollmannsberger, C. K.; Yuasa, T.; Srinivas, S.; Donskov, F.; Bamias, A.;
Wood, L. A.; Ernst, D. S.; Agarwal, N.; Vaishampayan, U. N.; Rha, S. Y.;
Kim, J. J. & Choueiri, T. K.
Cytoreductive nephrectomy in patients
with synchronous metastases from renal cell carcinoma: results from the
international metastatic renal cell carcinoma database consortium.
Eur Urol 2014,
66, 704-710.
G. Hudes, M. Carducci, P. Tomczak, J. Dutcher, R. Figlin, A. Kapoor,
E. Staroslawska, J. Sosman, D. McDermott, I. Bodrogi, Z. Kovacevic,
V. Lesovoy, I. G. H. Schmidt-Wolf, O. Barbarash, E. Gokmen, T. O’Toole,
S. Lustgarten, L. Moore, R. J. Motzer, and G. A. Trial.
Temsirolimus, interferon alfa, or both for advanced renal-cell
carcinoma.
N Engl J Med, 356 (22): 2271–2281, May 2007.
E. Jonasch et al., “Belzutifan for Renal Cell Carcinoma in von Hippel-Lindau Disease.,” NEJM, vol. 385, no. 22, pp. 2036–2046, 2021, doi: 10.1056/NEJMoa2103425.
Kattan u.a. 2001 KATTAN, M. W. ; REUTER, V. ; MOTZER, R. J. ; KATZ, J. ; RUSSO, P.: A postoperative prognostic nomogram for renal cell carcinoma.In: J Urol
166 (2001), Nr. 1, S. 63–7
Rana R. McKay u.a. Impact of angiotensin system inhibitors (ASI) on outcomes in patients (pts) with metastatic renal cell carcinoma (mRCC): Results from a pooled clinical trials database. J Clin Oncol 32, 2014 (suppl 4; abstr 437).
B. C. Leibovich, M. L. Blute, J. C. Cheville, C. M. Lohse, I. Frank, E. D.
Kwon, A. L. Weaver, A. S. Parker, und H. Zincke.
Prediction of progression after radical nephrectomy for patients with
clear cell renal cell carcinoma: a stratification tool for prospective
clinical trials.
Cancer, 97 (7): 1663–1671, Apr 2003.
doi: rm10.1002/cncr.11234.
URL https://dx.doi.org/10.1002/cncr.11234.
B. Ljungberg et al., “EAU Guidelines: Renal Cell Carcinoma.” (2024). https://uroweb.org/guidelines/renal-cell-carcinoma/
Mancuso und Sternberg 2005 MANCUSO, A. ;
STERNBERG, C. N.:
What’s new in the treatment of metastatic kidney cancer?
In: BJU Int
95 (2005), Nr. 9, S. 1171–80
Mickisch, G. H.; Garin, A.; van Poppel, H.; de Prijck,
L.; Sylvester, R.; , E. O. f. R. & of Cancer (EORTC) Genitourinary Group,
T.
Radical nephrectomy plus interferon-alfa-based immunotherapy
compared with interferon alfa alone in metastatic renal-cell carcinoma: a
randomised trial.
Lancet, 2001, 358, 966-970.
Motzer und Bukowski 2006 MOTZER, Robert J. ;
BUKOWSKI, Ronald M.:
Targeted therapy for metastatic renal cell carcinoma.
In: J Clin Oncol
24 (2006), Dec, Nr. 35, S. 5601–5608. -
URL https://dx.doi.org/10.1200/JCO.2006.08.5415
Motzer u.a. 2007 MOTZER, Robert J. ; HUTSON,
Thomas E. ; TOMCZAK, Piotr ; MICHAELSON, M. D. ;
BUKOWSKI, Ronald M. ; RIXE, Olivier ; OUDARD,
Stéphane ; NEGRIER, Sylvie ; SZCZYLIK, Cezary ;
KIM, Sindy T. ; CHEN, Isan ; BYCOTT, Paul W. ;
BAUM, Charles M. ; FIGLIN, Robert A.:
Sunitinib versus interferon alfa in metastatic renal-cell carcinoma.
In: N Engl J Med
356 (2007), Jan, Nr. 2, S. 115–124. -
URL https://dx.doi.org/10.1056/NEJMoa065044
Motzer, R. J.; Escudier, B.; McDermott, D. F.; George,
S.; Hammers, H. J.; Srinivas, S.; Tykodi, S. S.; Sosman, J. A.; Procopio,
G.; Plimack, E. R.; Castellano, D.; Choueiri, T. K.; Gurney, H.; Donskov,
F.; Bono, P.; Wagstaff, J.; Gauler, T. C.; Ueda, T.; Tomita, Y.; Schutz,
F. A.; Kollmannsberger, C.; Larkin, J.; Ravaud, A.; Simon, J. S.; Xu,
L.-A.; Waxman, I. M.; Sharma, P. & CheckMate025
Nivolumab versus
Everolimus in Advanced Renal-Cell Carcinoma.
New Engl J Med 2015, 373,
1803-1813.
Motzer, R. J.; Hutson, T. E.; Glen, H.;
Michaelson, M. D.; Molina, A.; Eisen, T.; Jassem, J.; Zolnierek, J.;
Maroto, J. P.; Mellado, B.; Melichar, B.; Tomasek, J.; Kremer, A.; Kim,
H.-J.; Wood, K.; Dutcus, C. & Larkin, J.
Lenvatinib, everolimus,
and the combination in patients with metastatic renal cell carcinoma: a
randomised, phase 2, open-label, multicentre trial.
The Lancet.
Oncology, 2015a, 16, 1473-1482.
R. J. Motzer, B. Escudier, S. Oudard, T. E. Hutson, C. Porta, S. Bracarda,
V. Gruenwald, J. A. Thompson, R. A. Figlin, N. Hollaender, G. Urbanowitz,
W. J. Berg, A. Kay, D. Lebwohl, und A. Ravaud.
Efficacy of everolimus in advanced renal cell carcinoma: a
double-blind, randomised, placebo-controlled phase iii trial.
Lancet, Jul 2008.
R. J. Motzer et al.“Tivozanib versus sorafenib as initial targeted therapy for patients with metastatic renal cell carcinoma: results from a phase III trial.,” Journal of clinical oncology : official journal of the American Society of Clinical Oncology, vol. 31, no. 30, pp. 3791–3799, 2013.
Motzer RJ, Escudier B, Choueiri TK et al. Final analysis of nivolumab plus cabozantinib for advanced renal cell carcinoma from the randomized phase III CheckMate 9ER trial. Ann Oncol. 2025 Sep 23:S0923-7534(25)04714-3. doi: 10.1016/j.annonc.2025.09.006.
S. Negrier, D. Perol, A. Ravaud, C. Chevreau, J. O. Bay, R. Delva, E. Sevin,
A. Caty, und B. Escudier.
Medroxyprogesterone, interferon alfa-2a, interleukin 2, or
combination of both cytokines in patients with metastatic renal carcinoma of
intermediate prognosis: results of a randomized controlled trial.
Cancer, 110 (11): 2468–2477, Dec 2007.
Powles, T.; Albiges, L.; Staehler, M.; Bensalah,
K.; Dabestani, S.; Giles, R. H.; Hofmann, F.; Hora, M.; Kuczyk, M. A.;
Lam, T. B.; Marconi, L.; Merseburger, A. S.; Fernández-Pello, S.; Tahbaz,
R.; Volpe, A.; Ljungberg, B. & Bex, A.
Updated European Association
of Urology Guidelines Recommendations for the Treatment of First-line
Metastatic Clear Cell Renal Cancer.
European urology, 2017
Rini, B. I.; Escudier, B.; Tomczak, P.; Kaprin, A.;
Szczylik, C.; Hutson, T. E.; Michaelson, M. D.; Gorbunova, V. A.; Gore, M.
E.; Rusakov, I. G.; Negrier, S.; Ou, Y.; Castellano, D.; Lim, H. Y.;
Uemura, H.; Tarazi, J.; Cella, D.; Chen, C.; Rosbrook, B.; Kim, S. &
Motzer, R. J.
Comparative effectiveness of axitinib versus sorafenib in
advanced renal cell carcinoma (AXIS): a randomised phase 3 trial.
Lancet,
2011, 378, 1931-1939.
Sternberg, C. N.; Davis, I. D.; Mardiak, J.; Szczylik,
C.; Lee, E.; Wagstaff, J.; Barrios, C. H.; Salman, P.; Gladkov, O. A.;
Kavina, A.; Zarbá, J. J.; Chen, M.; McCann, L.; Pandite, L.; Roychowdhury,
D. F. & Hawkins, R. E.
Pazopanib in locally advanced or metastatic
renal cell carcinoma: results of a randomized phase III trial.
2010,
28, 1061-1068.
Weight, C. J.; Larson, B. T.; Fergany, A. F.; Gao, T.; Lane, B. R.; Campbell, S. C.; Kaouk, J. H.; Klein, E. A. & Novick, A. C.
Nephrectomy induced chronic renal insufficiency is associated with increased risk of
cardiovascular death and death from any cause in patients with localized
cT1b renal masses.
J Urol, 2010, 183, 1317-1323
Zini, L.; Perrotte, P.; Capitanio, U.; Jeldres, C.; Shariat, S. F.; Antebi, E.; Saad, F.; Patard, J.; Montorsi, F. &
Karakiewicz, P. I.
Radical versus partial nephrectomy: effect on
overall and noncancer mortality.
Cancer, 2009, 115,
1465-1471
Zisman u.a. 2002 ZISMAN, A. ; PANTUCK, A. J. ;
WIEDER, J. ; CHAO, D. H. ; DOREY, F. ;
SAID, J. W. ; DEKERNION, J. B. ; FIGLIN, R. A. ;
BELLDEGRUN, A. S.:
Risk group assessment and clinical outcome algorithm to predict the
natural history of patients with surgically resected renal cell carcinoma.
In: J Clin Oncol
20 (2002), Nr. 23, S. 4559–66
 Deutsche Version: Nierenzellkarzinom
Urology-Textbook.com – Choose the Ad-Free, Professional Resource
This website is designed for physicians and medical professionals. It presents diseases of the genital organs through detailed text and images. Some content may not be suitable for children or sensitive readers. Many illustrations are available exclusively to Steady members. Are you a physician and interested in supporting this project? Join Steady to unlock full access to all images and enjoy an ad-free experience. Try it free for 7 days—no obligation.
New release: The first edition of the Urology Textbook as an e-book—ideal for offline reading and quick reference. With over 1300 pages and hundreds of illustrations, it’s the perfect companion for residents and medical students. After your 7-day trial has ended, you will receive a download link for your exclusive e-book.