You are here: Urology Textbook > Prostate > BPH > Diagnosis
Diagnosis of Benign Prostatic Hyperplasia and Benign Prostatic Syndrome
- Benign prostatic hyperplasia: definitions, epidemiology and etiology
- Benign prostatic hyperplasia: signs and symptoms
- Benign prostatic hyperplasia: diagnosis
- Benign prostatic hyperplasia: medical treatment
- Benign prostatic hyperplasia: surgical treatment
Principles of Diagnostic Workup
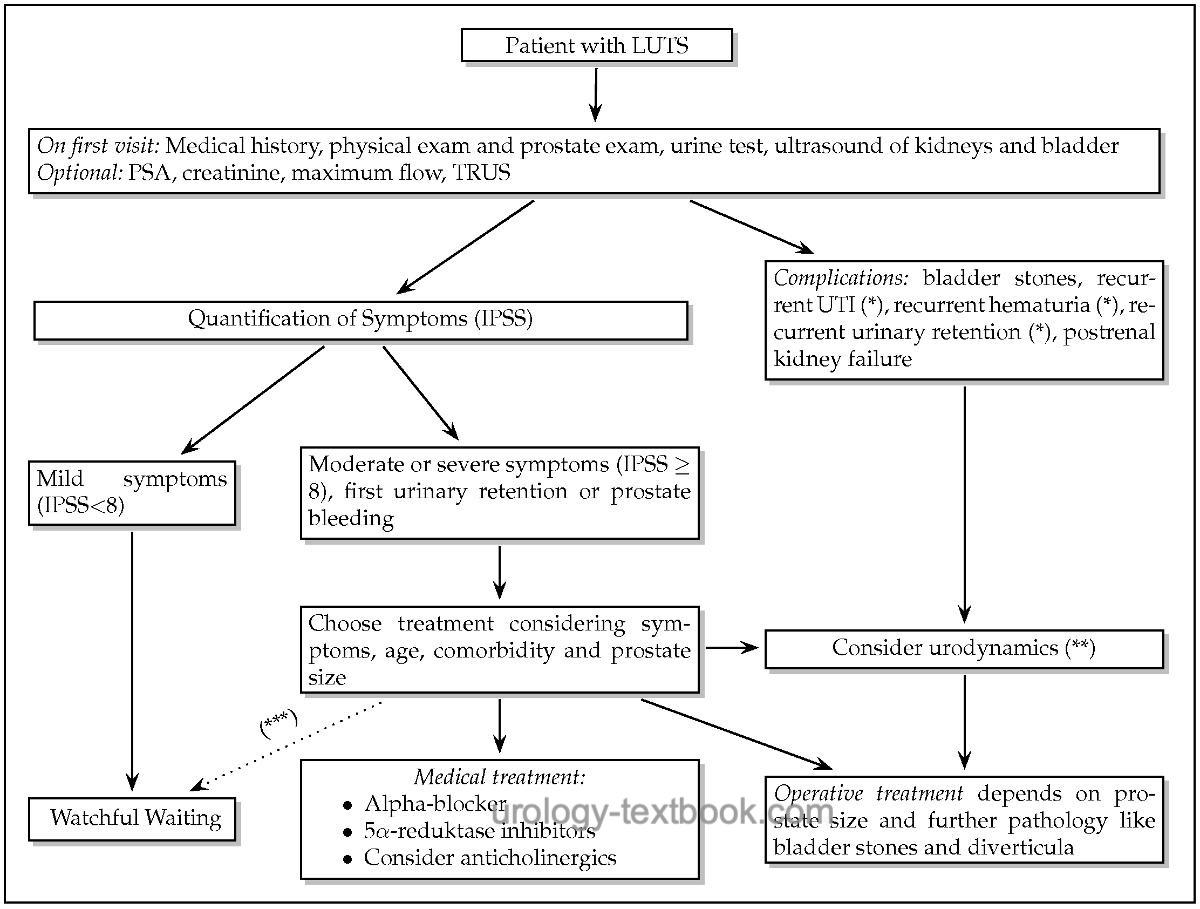
The diagnostic challenge is to determine the cause of voiding symptoms. Neither symptoms, urinary stream, nor prostate volume alone reliably predict prostate-related bladder outlet obstruction. The following algorithm presents a guideline-based approach to the diagnosis and treatment of lower urinary tract symptoms and benign prostatic syndrome.
 |
Medical History
The medical history assesses symptom severity, course, bother, fluid intake, nocturia, hematuria, urinary tract infections, urinary retention, neurologic disorders, previous surgery, sexual function, and treatment goals. It is central to the differential diagnosis of male lower urinary tract symptoms.
Risk Factors for Urethral Stricture
Urethritis, transurethral procedures, catheterization, pelvic or perineal trauma, and previous radiation therapy.
Neurogenic Bladder Disorders
Diabetes mellitus, Parkinson disease, multiple sclerosis, stroke, spinal cord disorders, and surgery involving the spinal canal or pelvis.
Medication
Sympathomimetics, anticholinergics, tricyclic antidepressants, antipsychotics, opioids, and antihistamines may worsen lower urinary tract symptoms or cause urinary retention.
Voiding Diary
A voiding diary for at least 2–3 days can document fluid intake, voiding frequency, voided volumes, and nocturnal polyuria. It is useful for the differential diagnosis of nocturia caused by diabetes, COPD, or heart failure.
Physical Examination
Physical examination includes the abdomen, external genitalia, meatus, and phimosis; digital rectal examination to estimate prostate size and identify suspicious induration; and, where indicated, a focused neurologic examination including sphincter tone, perineal sensation, saddle anesthesia, and paresis.
International Prostate Symptom Score
The International Prostate Symptom Score quantifies subjective symptoms.
Laboratory Studies
Urine Sediment
Perform urine sediment examination; obtain a urine culture if abnormalities are present.
Creatinine
Measure creatinine to exclude obstruction with upper urinary tract damage.
PSA
PSA helps distinguish between benign prostatic hyperplasia and prostate cancer and is useful in patients with a life expectancy exceeding 10 years. Evaluate elevated PSA values according to individual risk; the indication for biopsy depends on the overall risk, digital rectal examination, PSA kinetics, PSA density, and, where appropriate, multiparametric MRI. For a detailed discussion of PSA reference values and derived parameters, see PSA.
Further Diagnostic Tests
Uroflowmetry
For meaningful uroflowmetry, voided volume should exceed 150 ml. A maximum urinary flow below 10 ml/s is typical of benign prostatic syndrome, whereas a flow above 15 ml/s raises doubt about the benefit and necessity of surgical treatment. Uroflowmetry contributes little to the differential diagnosis of bladder outlet obstruction or bladder dysfunction.
Ultrasound
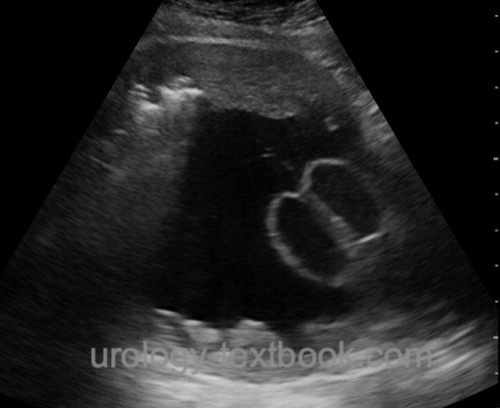
Ultrasound assesses postvoid residual urine, bladder wall and detrusor thickness, prostate size, intravesical middle lobe, bladder stones, bladder diverticula, and hydronephrosis.
 |
 |
Postvoid Residual Urine
Postvoid residual urine may promote recurrent urinary tract infections, bladder stones, and urinary retention. Single measurements have limited reliability because of substantial intraindividual variation. High postvoid residual volumes can result from both benign prostatic obstruction and detrusor underactivity; clear thresholds for surgery or failure of conservative treatment are lacking.
Kidneys
Assess the kidneys to exclude hydronephrosis, particularly in patients with elevated creatinine, urinary retention, high postvoid residual urine, recurrent infections, or flank pain.
Prostate Size
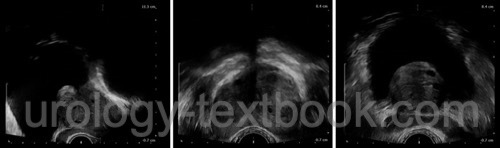
Determine prostate size transabdominally or by transrectal ultrasonography; it is important for selecting medical and invasive treatment options. Image the prostate in the sagittal and transverse planes, measure length, width, and height, and calculate prostate volume.
 |
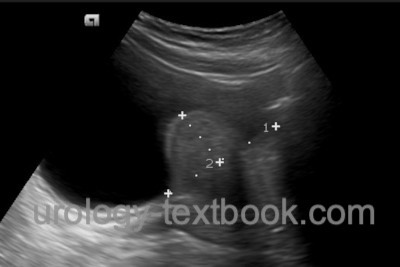
Intravesical Prostatic Protrusion
Measure intravesical prostatic protrusion in the sagittal plane with adequate bladder filling. Measure the perpendicular distance from the bladder base to the highest point of the prostatic middle lobe protruding into the bladder lumen. A protrusion exceeding 10 mm suggests relevant obstruction.
 |
Urodynamics
Uroflowmetry is part of the routine diagnostic workup; invasive urodynamics are reserved for selected uncertain cases. Consider urodynamics before invasive treatment in men younger than 50 years, men older than 80 years, patients with postvoid residual urine >300 ml, maximum urinary flow >15 ml/s, suspected neurogenic lower urinary tract dysfunction, previous radical pelvic surgery, or unsuccessful invasive treatment.
Despite adequate diagnostic assessment and patient selection, lower urinary tract symptoms persist in some patients after invasive treatment, usually because of storage symptoms, detrusor overactivity, or detrusor underactivity.
Cystoscopy
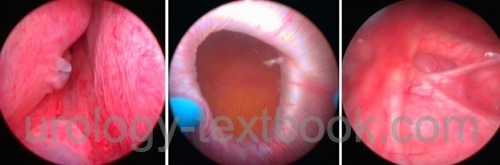
Cystoscopy is indicated for gross hematuria, suspected urethral stricture, bladder cancer, bladder stones, bladder diverticula, or before planned invasive treatment when endoscopic anatomy influences procedure selection. Cystoscopy should not be used as the sole basis for deciding on surgery. A large middle lobe, bladder bar, or kissing lateral lobes do not independently establish an indication for surgery.
 |
Radiologic Imaging
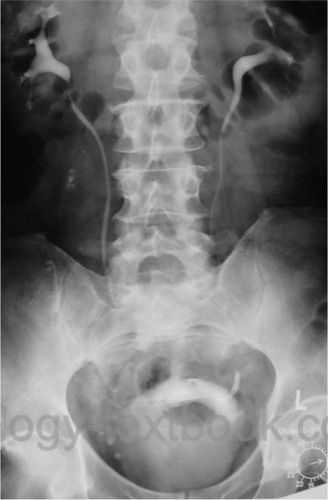
The urogram was long the standard investigation for evaluating the upper urinary tract before surgical treatment of benign prostatic syndrome. Today, ultrasound, laboratory testing, and targeted cross-sectional imaging have largely replaced it in routine diagnostics.
 |
CT or MR Urography
Indicated for unexplained gross hematuria, suspected tumor, urolithiasis, complex bladder diverticula, unexplained hydronephrosis, suspected extrinsic obstruction, or inconclusive ultrasonography.
Retrograde Urethrography
Indicated if urethral stricture is suspected.
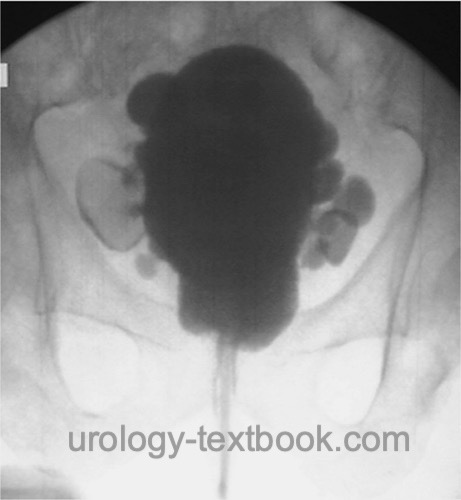
Cystography
Indicated if bladder diverticula or bladder stones are suspected.
 |
| BPH symptoms | Index | BPH treatment |
Index: 1–9 A B C D E F G H I J K L M N O P Q R S T U V W X Y Z
References
Andriole u.a. 2004 ANDRIOLE, G. L. ;
ROEHRBORN, C. ; SCHULMAN, C. ; SLAWIN, K. M. ;
SOMERVILLE, M. ; RITTMASTER, R. S.:
Effect of dutasteride on the detection of prostate cancer in men with
benign prostatic hyperplasia.
In: Urology
64 (2004), Nr. 3, S. 537–41; discussion 542–3
Burnett und Wein 2006 BURNETT, A. L. ; WEIN,
A. J.:
Benign prostatic hyperplasia in primary care: what you need to know.
In: J Urol
175 (2006), Nr. 3 Pt 2, S. S19–24
Chapple 2004 CHAPPLE, C. R.:
Pharmacological therapy of benign prostatic hyperplasia/lower urinary
tract symptoms: an overview for the practising clinician.
In: BJU Int
94 (2004), Nr. 5, S. 738–44
DGU Guideline, “S2e Leitlinie Diagnostik und Therapie des Benignen Prostatasyndroms (BPS).,” 2023. [Online]. Available: https://register.awmf.org/assets/guidelines/043-034l_S2e_Diagnostik_Therapie_benignes_Prostatasyndrom_2023-04.pdf
Donovan u.a. 2000 DONOVAN, J. L. ; PETERS,
T. J. ; NEAL, D. E. ; BROOKES, S. T. ; GUJRAL,
S. ; CHACKO, K. N. ; WRIGHT, M. ; KENNEDY, L. G. ;
ABRAMS, P.:
A randomized trial comparing transurethral resection of the prostate,
laser therapy and conservative treatment of men with symptoms associated with
benign prostatic enlargement: The CLasP study.
In: J Urol
164 (2000), Nr. 1, S. 65–70
“EAU Guideline: Non-neurogenic Male LUTS,” Available: https://uroweb.org/guidelines/treatment-of-non-neurogenic-male-luts/.
Kopp, R. P.; Freedland, S. J. & Parsons, J. K.
Associations
of benign prostatic hyperplasia with prostate cancer: the debate continues.
Eur
Urol, 2011, 60, 699-700; discussion 701-2.
Ørsted, D. D.; Bojesen, S. E.; Nielsen, S. F. &
Nordestgaard, B. G.
Association of clinical benign prostate hyperplasia
with prostate cancer incidence and mortality revisited: a nationwide
cohort study of 3,009,258 men.
Eur Urol, 2011, 60,
691-698.
Parsons, J. Kellogg; Messer, Karen; White, Martha;
Barrett-Connor, Elizabeth; Bauer, Douglas C; Marshall, Lynn M; in Men
(MrOS) Research Group, Osteoporotic Fractures & the Urologic Diseases in
America Project
Obesity increases and physical activity decreases lower
urinary tract symptom risk in older men: the Osteoporotic Fractures in Men
study.
Eur Urol, 2011, 60, 1173-1180.
Reich u.a. 2006 REICH, O. ; GRATZKE, C. ;
STIEF, C. G.:
Techniques and long-term results of surgical procedures for BPH.
In: Eur Urol
49 (2006), Nr. 6, S. 970–8; discussion 978
Uygur u.a. 1998 UYGUR, M. C. ; GUR, E. ;
ARIK, A. I. ; ALTUG, U. ; EROL, D.:
Erectile dysfunction following treatments of benign prostatic
hyperplasia: a prospective study.
In: Andrologia
30 (1998), Nr. 1, S. 5–10
 Deutsche Version: Diagnostik der benignen Prostatahyperplasie
Urology-Textbook.com – Choose the Ad-Free, Professional Resource
This website is designed for physicians and medical professionals. It presents diseases of the genital organs through detailed text and images. Some content may not be suitable for children or sensitive readers. Many illustrations are available exclusively to Steady members. Are you a physician and interested in supporting this project? Join Steady to unlock full access to all images and enjoy an ad-free experience. Try it free for 7 days—no obligation.
New release: The first edition of the Urology Textbook as an e-book—ideal for offline reading and quick reference. With over 1300 pages and hundreds of illustrations, it’s the perfect companion for residents and medical students. After your 7-day trial has ended, you will receive a download link for your exclusive e-book.