You are here: Urology Textbook > Prostate > Prostate cancer > Definition
Prostate Cancer: Epidemiology and Etiology
- Prostate cancer: Epidemiology and etiology
- Prostate cancer: Pathology
- Prostate cancer: Signs and symptoms
- Prostate cancer: Screening
- Prostate cancer: Staging
- Prostate cancer: Treatment options
- Prostate cancer: Active surveillance
- Prostate cancer: Prostatectomy
- Prostate cancer: Radiation therapy
- Prostate cancer: Brachytherapy
- Prostate cancer: TURP and experimental treatment options
- Prostate cancer: Hormonal therapy of advanced prostate cancer
- Prostate cancer: Treatment of castration-resistant prostate cancer
Guidelines and review literature: (EAU Guidelines Prostate Cancer) (S3-Leitlinie Prostatakarzinom) (Walsh-Campbell Urology).
Definition of Prostate Cancer
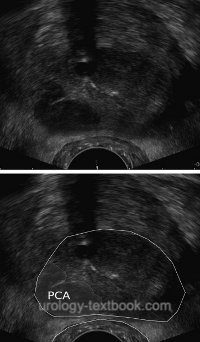
Prostate cancer is a malignant epithelial-glandular neoplasm of the prostate; acinar adenocarcinoma is the predominant histologic type. Its clinical course ranges from indolent, localized tumors to rapidly progressive metastatic disease.
 |
Epidemiology
Cancer statistics:
In Germany, prostate cancer is the most common cancer in men (approximately 25 % of newly diagnosed cancers) and ranks second among causes of cancer death. An estimated 79 600 new cases were diagnosed in 2023, and 15 200 men died from prostate cancer in the same year. The age-standardized incidence was 111 per 100 000, and the age-standardized mortality was 17.3 per 100 000 (Robert Koch Institute, 2025).
Age at diagnosis:
The median age at diagnosis is approximately 72 years, and the median age at death is 82 years. The annual incidence rises sharply with age; prostate cancer before 50 years of age is very rare. Long survival after diagnosis is common; comparative intervention trials using overall survival as an endpoint are therefore methodologically difficult.
Worldwide incidence:
Incidence shows marked geographic and ethnic variation. According to SEER data for 2019–2023, the age-adjusted incidence in the United States is approximately 200 per 100 000 in non-Hispanic Black men, 122 per 100 000 in non-Hispanic White men, 93 per 100 000 in Hispanic men, 87 per 100 000 in American Indian or Alaska Native men, and 67 per 100 000 in Asian men.
Prevalence:
Autopsy studies demonstrate a high prevalence of histologically detectable, often clinically insignificant prostate cancers in older men. A substantial proportion of these tumors remain asymptomatic throughout life and do not cause death. This discrepancy between histologic prevalence and clinical relevance explains why overdiagnosis and overtreatment are central challenges of early detection.
Etiology
Carcinogenesis is multifactorial. Established risk factors include age, family history, pathogenic germline variants, and African ancestry. Lifestyle and environmental factors modify risk, but no individual measure has been proven to provide specific primary prevention.
Genetic Predisposition
Ethnicity:
The incidence of prostate cancer differs markedly according to genetic ancestry and migration history. Men of African ancestry have the highest risk. Asian men have a low incidence in Asian countries of origin; after migration to Western countries, incidence increases markedly but, on average, remains lower than in non-Hispanic White men in the United States. This supports an interaction between genetic susceptibility and non-genetic factors.
Familial prostate cancer:
Familial prostate cancer is defined by at least three affected relatives or at least two relatives diagnosed before 55 years of age. Risk is substantially increased in men with affected first-degree relatives and rises further with the number of affected relatives and younger age at diagnosis in the family. Offer genetic counseling to men with early-onset disease or a suspicious family history.
Molecular alterations:
Most prostate cancers arise through an interplay of somatic alterations, germline risk variants, and epigenetic changes. Frequently described alterations include PI3K/AKT signaling, PTEN loss, DNA methylation, and changes involving MYC, TP53, RB1, DNA repair genes, androgen receptor signaling pathways, angiogenesis, and the tumor microenvironment.
Chronic Inflammation
Chronic inflammation, oxidative stress, and inflammation-associated glandular atrophy are discussed as possible cofactors in carcinogenesis. Observational studies have partly shown a reduced risk with acetylsalicylic acid, but prospective data are unavailable.
Testosterone and Androgen Receptor
Androgens are essential for the survival, growth, and function of normal prostate cells. In the absence of testosterone, for example in eunuchs, the prostate atrophies, largely preventing the development of prostate cancer. Nevertheless, endogenous testosterone is not considered a direct initiator of carcinogenesis. The saturation hypothesis proposes that above low androgen levels, there is no linear association between testosterone concentration and prostate cancer risk. Prostate cancer is androgen dependent at many stages; accordingly, androgen deprivation slows progression in advanced disease. Polymorphisms and alterations of the androgen receptor may influence disease biology and treatment resistance.
Environmental Factors
The increase in incidence after migration from low-incidence to high-incidence regions supports a role for non-genetic factors in prostate carcinogenesis. In particular, obesity, metabolic risk factors, physical inactivity, and a Western dietary pattern are associated with prostate cancer.
Diet:
Many dietary components have been associated with prostate cancer in both favorable and unfavorable directions (Masko et al., 2013). However, no specific diet can be recommended to prevent prostate cancer. General prevention recommendations apply: maintain a healthy body weight, exercise regularly, eat a predominantly plant-based diet, and reduce alcohol consumption.
Selenium deficiency:
Low selenium levels have been associated with increased prostate cancer risk in observational studies. The large randomized SELECT trial did not demonstrate a preventive effect.
Soy-rich diet:
Soy products and isoflavones, including genistein, daidzein, and glycitein, have been associated with a lower risk of prostate cancer (Zhang et al., 2016).
Vitamin D:
Low vitamin D levels are associated in observational studies with unfavorable health parameters and, in some studies, with a poorer prognosis of prostate cancer. However, vitamin D supplementation for primary prevention of prostate cancer has not been proven. Supplementation is appropriate in patients with documented deficiency, increased fracture risk, osteoporosis, or androgen deprivation.
Tomatoes:
A lycopene-rich diet, for example through tomato products, has been associated with a lower risk of prostate cancer in observational studies.
Smoking:
Smoking is not an established risk factor for the overall incidence of prostate cancer, but it is associated with more advanced tumor stage, a higher risk of recurrence, and increased prostate cancer-specific mortality.
Cardiovascular risk factors:
Obesity, metabolic syndrome, diabetes mellitus, and physical inactivity are associated with less favorable tumor biology, a higher risk of progression, and increased overall mortality.
Alcohol consumption:
Alcohol increases the general risk of cancer. Data for prostate cancer are inconsistent.
Vasectomy:
A possible small association between vasectomy and prostate cancer may be explained by detection bias, more frequent urologic consultations, and PSA testing; a causal association has not been established. A recent meta-analysis found no association (Bhindi et al., 2017).
Sexuality:
Observational data regarding early sexual activity, ejaculation frequency, and sexually transmitted infections are heterogeneous.
Other environmental factors:
Data regarding pesticides, polychlorinated biphenyls, occupational exposures, and electromagnetic fields are conflicting.
| Seminal vesicle cyst | Index | Prostate cancer: pathology |
Index: 1–9 A B C D E F G H I J K L M N O P Q R S T U V W X Y Z
References
Bratt 2002 BRATT, O.:
Hereditary prostate cancer: clinical aspects.
In: J Urol
168 (2002), Nr. 3, S. 906–13
N. Mottet (Chair), J. Bellmunt, E. Briers (Patient Representative), R.C.N. van den Bergh (Guidelines Associate), M. Bolla, N.J. van Casteren (Guidelines Associate), P. Cornford, S. Culine, S. Joniau, T. Lam, M.D. Mason, V. Matveev, H. van der Poel, T.H. van der Kwast, O. Rouvière, T. Wiegel Guidelines on Prostate Cancer of the European Association of Urology (EAU), https://uroweb.org/guidelines/prostate-cancer/.
DeMarzo u.a. 2003 DEMARZO, A. M. ; NELSON,
W. G. ; ISAACS, W. B. ; EPSTEIN, J. I.:
Pathological and molecular aspects of prostate cancer.
In: Lancet
361 (2003), Nr. 9361, S. 955–64
Gronberg 2003 GRONBERG, H.:
Prostate cancer epidemiology.
In: Lancet
361 (2003), Nr. 9360, S. 859–64
Kenfield, S. A.; Stampfer, M. J.; Chan, J. M. &
Giovannucci, E.
Smoking and prostate cancer survival and recurrence.
JAMA,
2011, 305, 2548-2555
Masko, E. M.; Allott, E. H. & Freedland, S. J.
The relationship between nutrition and prostate cancer: is more always better?
Eur
Urol, 2013, 63, 810-820.
Wein, A. J.; Kavoussi, L. R.; Partin, A. P. & Peters, C. A.
Campbell-Walsh Urology
. Elsevier, 2015. ISBN 978-1455775675.
Zhang, H.-Y.; Cui, J.; Zhang, Y.; Wang, Z.-L.; Chong,
T. & Wang, Z.-M.
Isoflavones and Prostate Cancer: A Review of Some
Critical Issues.
Chin Med J (Engl), 2016, 129,
341-347
Robert-Koch-Institut Krebs in Deutschland. www.krebsdaten.de
 Deutsche Version: Prostatakarzinom
Urology-Textbook.com – Choose the Ad-Free, Professional Resource
This website is designed for physicians and medical professionals. It presents diseases of the genital organs through detailed text and images. Some content may not be suitable for children or sensitive readers. Many illustrations are available exclusively to Steady members. Are you a physician and interested in supporting this project? Join Steady to unlock full access to all images and enjoy an ad-free experience. Try it free for 7 days—no obligation.
New release: The first edition of the Urology Textbook as an e-book—ideal for offline reading and quick reference. With over 1300 pages and hundreds of illustrations, it’s the perfect companion for residents and medical students. After your 7-day trial has ended, you will receive a download link for your exclusive e-book.