You are here: Urology Textbook > Prostate > Prostate cancer > Staging
Prostate Cancer: Diagnosis and Staging
- Prostate cancer: Epidemiology and etiology
- Prostate cancer: Pathology
- Prostate cancer: Signs and symptoms
- Prostate cancer: Screening
- Prostate cancer: Staging
- Prostate cancer: Treatment options
- Prostate cancer: Active surveillance
- Prostate cancer: Prostatectomy
- Prostate cancer: Radiation therapy
- Prostate cancer: Brachytherapy
- Prostate cancer: TURP and experimental treatment options
- Prostate cancer: Hormonal therapy of advanced prostate cancer
- Prostate cancer: Treatment of castration-resistant prostate cancer
Guidelines and review literature: (EAU Guidelines Prostate Cancer) (S3-Leitlinie Prostatakarzinom) (Walsh-Campbell Urology).
Assessment of tumor stage and biological aggressiveness is crucial for treatment decisions in prostate cancer. Diagnostic evaluation includes digital rectal examination (DRE), PSA concentration, prostate biopsy histology, laboratory tests, imaging, and, in selected cases, pelvic lymphadenectomy.
Clinical Staging of Prostate Cancer
Digital rectal examination, PSA concentration, and Gleason grade each correlate well with the pathological tumor stage. However, the predictive accuracy of an individual parameter is too low for a given patient. Combining these variables allows reliable estimation of clinical risk (prostate cancer mortality) [Table D’Amico risk classification].
| Risk | Criteria | 10-year mortality after EBRT (*) | 10-year mortality after RPE (*) |
|---|---|---|---|
| Low | PSA < 10 ng/ml and Gleason score ≤ 6 | 2% | 1% |
| Intermediate | PSA 10–20 ng/ml or Gleason score 7 | 8% | 4% |
| High | PSA > 20 ng/ml or Gleason score ≥ 8 | 24% | 11% |
Additional consideration of tumor burden in the biopsy and other clinical parameters further improves predictive accuracy. The CAPRA score is suitable for this purpose [Table CAPRA score]. CAPRA stands for Cancer of the Prostate Risk Assessment and was developed at the University of California, San Francisco, using data from the CaPSURE study (Cooperberg et al., 2009). Table pathological outcomes and prognosis after radical prostatectomy shows the results according to the CAPRA score.
| Risk factor | Criteria | Points |
|---|---|---|
| Age | < 50 years | 0 |
| ≥ 50 years | 1 | |
| PSA at diagnosis | ≤ 6 ng/ml | 0 |
| 6.1–10 ng/ml | 1 | |
| 10.1–20 ng/ml | 2 | |
| 20.1–30 ng/ml | 3 | |
| > 30 ng/ml | 4 | |
| Biopsy Gleason score | No pattern 4 or 5 | 0 |
| Secondary pattern 4 or 5 | 1 | |
| Primary pattern 4 or 5 | 3 | |
| Clinical stage | T1–T2 | 0 |
| ≥ T3a | 1 | |
| Positive biopsy cores | < 34% | 0 |
| ≥ 34% | 1 |
| CAPRA score | 0–1 | 2 | 3 | 4 | 5 | 6 | > 7 |
|---|---|---|---|---|---|---|---|
| Positive surgical margin | 8–24 | 15–26 | 16–31 | 18–42 | 26–44 | 44–53 | 42–58 |
| Extraprostatic extension | 6–14 | 16–19 | 23–26 | 26–40 | 44–55 | 51–56 | 68–86 |
| Seminal vesicle invasion | 1–2 | 3–4 | 4–6 | 9–11 | 13–21 | 22 | 27–47 |
| Lymph node metastases | 0–1 | 1–3 | 2 | 1–4 | 3–11 | 4–11 | 3–34 |
| Progression-free at 3 years | 92–95 | 84–95 | 76–87 | 73–82 | 67–70 | 46–72 | 35–50 |
| Progression-free at 5 years | 86–91 | 75–91 | 65–83 | 60–74 | 52–61 | 29–62 | 20–30 |
The Partin tables combine local tumor stage, PSA concentration, and Gleason score to estimate the risk of extraprostatic extension, seminal vesicle invasion, and lymph node metastases. Some authors consider that the tables underestimate lymph node metastasis risk because of the limited lymphadenectomy template used in the clinical series.
The Kattan nomograms of the Memorial Sloan Kettering Cancer Center likewise combine local tumor stage, PSA concentration, and Gleason score. They estimate 10-year progression-free survival after radical prostatectomy and 15-year cancer-specific survival.
Bone Scintigraphy
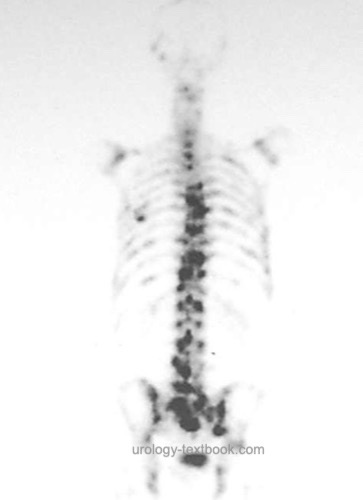
Bone scintigraphy is a conventional staging modality for bone metastases with relatively high sensitivity but limited specificity [Figure bone metastases in prostate cancer]. Indeterminate findings should be evaluated by MRI, CT, or conventional radiography according to their location and the clinical question; bone biopsy should be considered when uncertainty remains.
Bone scintigraphy should be omitted in patients with a PSA concentration below 10 ng/ml, Gleason score below 8, clinically localized disease, and no bone pain.
 |
Computed Tomography
CT is indicated in advanced prostate cancer, either in combination with bone scintigraphy or as part of a PET/CT examination. CT can detect enlarged lymph nodes, bone metastases, hydronephrosis, and infiltration of adjacent organs. In asymptomatic patients with a PSA concentration below 20 ng/ml and a Gleason score below 8, treatment-relevant pathological findings are uncommon.
Positron Emission Tomography
The main indications for PSMA-PET/CT are high-risk prostate cancer, biochemical recurrence after curative treatment, and progression during systemic therapy for metastatic prostate cancer. PET combined with CT or MRI provides very high diagnostic accuracy and is superior to the combination of bone scintigraphy and CT (Bukavina et al., 2023). Tracers include 68Ga-PSMA and 18F-labeled PSMA ligands.
Multiparametric MRI of the Prostate
Multiparametric MRI of the prostate is indicated for imaging locally advanced prostate cancer when imaging findings may alter the treatment decision [Figure multiparametric MRI in pT3b prostate cancer].
Pelvic Lymphadenectomy
Pelvic lymphadenectomy is a surgical staging procedure when there is a relevant probability of lymph node metastases and is usually performed during radical prostatectomy. Historically, isolated surgical lymph node staging was discussed before perineal prostatectomy or brachytherapy; it is no longer routinely indicated. Indications and extent are discussed in the section on radical prostatectomy. See also laparoscopic pelvic lymphadenectomy for technique and complications.
Experimental Diagnostic Methods
New Screening or Tumor Markers
PCA3:
PCA3 (prostate cancer antigen 3) is a non-protein-coding RNA that is overexpressed in prostate cancer and can be detected in urine after prostatic massage. PCA3 may provide additional information in selected patients with an elevated PSA concentration and a previous negative biopsy, but it is not a standard test for population-based early detection.
Analysis of Gene Expression:
Tissue-based gene-expression and genomic-classifier tests, such as Prolaris, Decipher Prostate, or the Genomic Prostate Score, may provide additional prognostic information in selected patients with localized prostate cancer. They are used mainly to estimate tumor aggressiveness and to support treatment decisions, for example active surveillance versus curative treatment. Routine use is not recommended.
Other Methods:
Other experimental approaches include detection of micrometastases in bone marrow and RT-PCR for detecting prostate cancer cells in blood or lymph nodes.
Imaging
New methods, including PET, MRI with specialized contrast agents, and specialized ultrasound techniques, are being evaluated in clinical series.
Micro-ultrasound:
Targeted prostate biopsy using a high-resolution TRUS probe (ExactVu, 29 MHz) may support detection of clinically significant prostate cancer (Dariane et al., 2022). The method is promising but does not currently replace guideline-based mpMRI-guided and systematic diagnostic evaluation.
Elastography:
Ultrasound elastography displays the elasticity of prostate tissue in color by applying pressure with an ultrasound probe. Less elastic regions are suspicious for cancer. However, sensitivity and specificity are insufficient to omit systematic or mpMRI-targeted prostate biopsy.
Analysis of Ultrasonography Raw Data:
Database-assisted analysis of ultrasound raw data, such as HistoScanning, was developed to improve prostate cancer detection. Independent studies have not demonstrated sufficient sensitivity and specificity for routine clinical use.
| Prostate cancer screening | Index | Prostate cancer treatment options |
Index: 1–9 A B C D E F G H I J K L M N O P Q R S T U V W X Y Z
References
Afshar-Oromieh, A.; Haberkorn, U.; Schlemmer, H. P.;
Fenchel, M.; Eder, M.; Eisenhut, M.; Hadaschik, B. A.; Kopp-Schneider, A.
& Röthke, M.
Comparison of PET/CT and PET/MRI hybrid systems
using a 68Ga-labelled PSMA ligand for the diagnosis of recurrent prostate
cancer: initial experience.
Eur J Nucl Med Mol Imaging, 2014,
41, 887-897
Auprich, M.; Bjartell, A.; Chun, F. K.; de la Taille,
A.; Freedland, S. J.; Haese, A.; Schalken, J.; Stenzl, A.; Tombal, B. &
van der Poel, H.
Contemporary role of prostate cancer antigen 3 in the
management of prostate cancer.
Eur Urol, 2011, 60,
1045-1054.
Brock, M.; von Bodman, C.; Palisaar, R. J.; Löppenberg,
B.; Sommerer, F.; Deix, T.; Noldus, J. & Eggert, T.
The Impact of
Real-Time Elastography Guiding a Systematic Prostate Biopsy to Improve
Cancer Detection Rate: A Prospective Study of 353 Patients.
J Urol, 2012.
D'Amico, A. V.; Moul, J.; Carroll, P. R.; Sun, L.;
Lubeck, D. & Chen, M.
Cancer-specific mortality after surgery or
radiation for patients with clinically localized prostate cancer managed
during the prostate-specific antigen era.
J Clin Oncol, 2003,
21, 2163-2172.
D'Amico, A. V.; Hui-Chen, M.; Renshaw, A. A.; Sussman,
B.; Roehl, K. A. & Catalona, W. J.
Identifying men diagnosed with
clinically localized prostate cancer who are at high risk for death from
prostate cancer.
J Urol, 2006, 176, S11-S15.
Guidelines on Prostate Cancer of the European Association of Urology (EAU), https://uroweb.org/guidelines/prostate-cancer/.
Harisinghani u.a. 2003 HARISINGHANI, M. G. ;
BARENTSZ, J. ; HAHN, P. F. ; DESERNO, W. M. ;
TABATABAEI, S. ; KAA, C. H. van de ; ROSETTE, J.
de la ; WEISSLEDER, R.:
Noninvasive detection of clinically occult lymph-node metastases in
prostate cancer.
In: N Engl J Med
348 (2003), Nr. 25, S. 2491–9
Javed, S.; Chadwick, E.; Edwards, A. A.; Beveridge, S.;
Laing, R.; Bott, S.; Eden, C. & Langley, S.
Does prostate
HistoScanning™ play a role in detecting prostate cancer in routine
clinical practice? Results from three independent studies.
BJU Int, 2014,
114, 541-548
Kattan u.a. 1998 KATTAN, M. W. ; EASTHAM,
J. A. ; STAPLETON, A. M. ; WHEELER, T. M. ;
SCARDINO, P. T.:
A preoperative nomogram for disease recurrence following radical
prostatectomy for prostate cancer.
In: J Natl Cancer Inst
90 (1998), Nr. 10, S. 766–71
Kattan u.a. 2001 KATTAN, M. W. ; POTTERS, L. ;
BLASKO, J. C. ; BEYER, D. C. ; FEARN, P. ;
CAVANAGH, W. ; LEIBEL, S. ; SCARDINO, P. T.:
Pretreatment nomogram for predicting freedom from recurrence after
permanent prostate brachytherapy in prostate cancer.
In: Urology
58 (2001), Nr. 3, S. 393–9
Kattan u.a. 2003 KATTAN, M. W. ; ZELEFSKY,
M. J. ; KUPELIAN, P. A. ; CHO, D. ; SCARDINO,
P. T. ; FUKS, Z. ; LEIBEL, S. A.:
Pretreatment nomogram that predicts 5-year probability of metastasis
following three-dimensional conformal radiation therapy for localized
prostate cancer.
In: J Clin Oncol
21 (2003), Nr. 24, S. 4568–71
Perdonà, S.; Cavadas, V.; Lorenzo, G. D.; Damiano, R.;
Chiappetta, G.; Prete, P. D.; Franco, R.; Azzarito, G.; Scala, S.; Arra,
C.; Sio, M. D. & Autorino, R.
Prostate Cancer Detection in the
"Grey Area" of Prostate-Specific Antigen Below 10 ng/ml: Head-to-Head
Comparison of the Updated PCPT Calculator and Chun's Nomogram, Two Risk
Estimators Incorporating Prostate Cancer Antigen 3.
Eur Urol, 2010
Leitlinienprogramm Onkologie (Deutsche Krebsgesellschaft, Deutsche Krebshilfe, AWMF): Interdisziplinäre Leitlinie der Qualität S3 zur Früherkennung, Diagnose und Therapie der verschiedenen Stadien des Prostatakarzinoms, https://www.leitlinienprogramm-onkologie.de/leitlinien/prostatakarzinom
Wein, A. J.; Kavoussi, L. R.; Partin, A. P. & Peters, C. A.
Campbell-Walsh Urology
. Elsevier, 2015. ISBN 978-1455775675.
Sanz u.a. 2004 SANZ, G. ; RIOJA, J. ;
ZUDAIRE, J. J. ; BERIAN, J. M. ; RICHTER, J. A.:
PET and prostate cancer.
In: World J Urol
22 (2004), Nr. 5, S. 351–2
Schiffmann, J.; Tennstedt, P.; Fischer, J.; Tian, Z.;
Beyer, B.; Boehm, K.; Sun, M.; Gandaglia, G.; Michl, U.; Graefen, M. &
Salomon, G.
Does HistoScanning™ predict positive results in prostate
biopsy? A retrospective analysis of 1,188 sextants of the prostate.
World
J Urol, 2014, 32, 925-930.
Smaletz u.a. 2002 SMALETZ, O. ; SCHER, H. I. ;
SMALL, E. J. ; VERBEL, D. A. ; MCMILLAN, A. ;
REGAN, K. ; KELLY, W. K. ; KATTAN, M. W.:
Nomogram for overall survival of patients with progressive metastatic
prostate cancer after castration.
In: J Clin Oncol
20 (2002), Nr. 19, S. 3972–82
Wawroschek u.a. 2003 WAWROSCHEK, Friedhelm ;
WAGNER, Theodor ; HAMM, Michael ; WECKERMANN,
Dorothea ; VOGT, Harry ; MäRKL, Bruno ; GORDIJN,
Ronald ; HARZMANN, Rolf:
The influence of serial sections, immunohistochemistry, and extension
of pelvic lymph node dissection on the lymph node status in clinically
localized prostate cancer.
In: Eur Urol
43 (2003), Feb, Nr. 2, S. 132–6; discussion 137
 Deutsche Version: Prostatakarzinom
Urology-Textbook.com – Choose the Ad-Free, Professional Resource
This website is designed for physicians and medical professionals. It presents diseases of the genital organs through detailed text and images. Some content may not be suitable for children or sensitive readers. Many illustrations are available exclusively to Steady members. Are you a physician and interested in supporting this project? Join Steady to unlock full access to all images and enjoy an ad-free experience. Try it free for 7 days—no obligation.
New release: The first edition of the Urology Textbook as an e-book—ideal for offline reading and quick reference. With over 1300 pages and hundreds of illustrations, it’s the perfect companion for residents and medical students. After your 7-day trial has ended, you will receive a download link for your exclusive e-book.