You are here: Urology Textbook > Prostate > Prostate cancer > Definition
Castration-Resistant Prostate Cancer (CRPC)
- Prostate cancer: Epidemiology and etiology
- Prostate cancer: Pathology
- Prostate cancer: Signs and symptoms
- Prostate cancer: Screening
- Prostate cancer: Staging
- Prostate cancer: Treatment options
- Prostate cancer: Active surveillance
- Prostate cancer: Prostatectomy
- Prostate cancer: Radiation therapy
- Prostate cancer: Brachytherapy
- Prostate cancer: TURP and experimental treatment options
- Prostate cancer: androgen deprivation therapy of advanced prostate cancer
- Prostate cancer: Treatment of castration-resistant prostate cancer
Guidelines and review literature: (EAU Guidelines Prostate Cancer) (S3-Leitlinie Prostatakarzinom) (Walsh-Campbell Urology).
Definition and Diagnosis of Castration-Resistant Prostate Cancer
Castration-resistant prostate cancer (CRPC) is advanced prostate cancer with biochemical progression (rising PSA concentration) or radiologic progression despite effective androgen deprivation.
- M0 CRPC: Biochemical progression during effective androgen deprivation without metastases on conventional imaging
- High-risk M0 CRPC: M0 CRPC with a PSA doubling time below 10 months
- M1 CRPC: Radiologic progression despite effective androgen deprivation
Mechanisms of castration resistance:
- Changes in the androgen receptor, including gene amplification and overexpression
- Overexpression of the antiapoptotic gene Bcl-2
- Activation of androgen-independent intracellular signaling pathways for proliferation
- Androgen receptor cofactors that increase receptor activity
- Intracellular synthesis of testosterone from cholesterol
Since castration-resistant prostate cancer remains hormone dependent, the outdated term hormone-refractory prostate cancer should no longer be used. Continue androgen deprivation despite castration resistance; it is the foundation of the systemic treatments listed below (see androgen deprivation therapy of advanced prostate cancer).
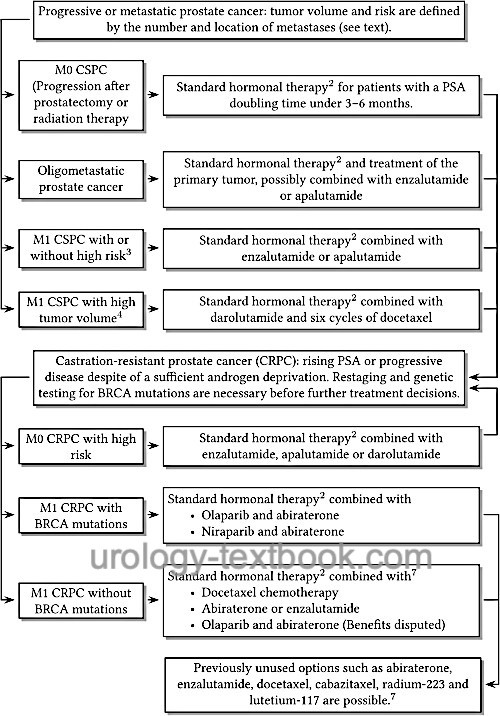 |
Diagnosis of CRPC
Confirm effective medical castration by measuring the serum testosterone concentration.
Imaging:
CT of the abdomen and chest and bone scintigraphy remain the standard investigations for detecting metastases. PSMA-PET detects metastases earlier; however, the recommendations and study results below for M0 and M1 CRPC are predominantly based on conventional imaging. Repeat imaging if the disease progresses.
Laboratory tests:
Measure the PSA concentration every three months. Depending on symptoms or suspected progression, also obtain a complete blood count, electrolytes, creatinine, liver enzymes, and alkaline phosphatase.
Treatment of Castration-Resistant Prostate Cancer
PARP Inhibitors
Poly(ADP-ribose) polymerase (PARP) participates in cellular DNA repair. In the pivotal trial, the PARP inhibitor olaparib showed a marked response in patients with BRCA mutations and CRPC progressing on enzalutamide or abiraterone: prolonged progression-free survival (7 vs. 4 months) and overall survival (19 vs. 15 months) (Bono et al., 2020). The main adverse effects are anemia and nausea. Olaparib has been approved in Europe since 2020; requirements are CRPC progression during androgen receptor pathway inhibitor treatment and evidence of BRCA1/2 mutations.
Olaparib combined with abiraterone/prednisolone:
The PROpel trial showed prolonged progression-free survival (25 vs. 17 months) and overall survival (42 vs. 35 months) in patients with M1 CRPC who were not eligible for chemotherapy, irrespective of BRCA mutation status (Saad et al., 2023). In the subgroup analysis, patients without BRCA mutations had only a small overall-survival benefit (HR 0.91; 40 vs. 38 months), whereas the difference was pronounced in patients with BRCA mutations (HR 0.29). Abiraterone, prednisolone, and olaparib have been approved in Europe since 2023 as first-line treatment for M1 CRPC without mandatory genetic testing. In the United States, approval is limited to patients with BRCA mutations because of concerns about the risk-benefit ratio in patients without BRCA mutations.
Niraparib combined with abiraterone:
The MAGNITUDE trial showed prolonged progression-free survival in patients with CRPC and BRCA mutations for whom chemotherapy was not indicated (20 vs. 11 months) (Chi et al., 2023). Patients with other HRR gene mutations also benefited (17 vs. 14 months). Overall-survival analysis has not yet shown a difference. The fixed combination Akeega (niraparib/abiraterone 100 mg/500 mg, two tablets daily) has been approved in Europe since 2023 for first-line treatment of CRPC with BRCA mutations; prescribe prednisolone in addition.
Talazoparib combined with enzalutamide:
The TALAPRO-2 trial showed prolonged progression-free survival with talazoparib combined with enzalutamide in patients with CRPC (HR 0.63) (Agarwal et al., 2023). Overall-survival data are not yet available. In the subgroup analysis, the benefit was substantially smaller in patients without BRCA mutations (HR 0.70), whereas the difference was pronounced in patients with BRCA mutations (HR 0.20). Talazoparib combined with enzalutamide has been approved in Europe since 2024 for first-line treatment of CRPC when chemotherapy is not clinically indicated. BRCA mutation testing is not mandatory in Europe; in the United States, talazoparib is approved only for patients with BRCA mutations. The recommended dose is talazoparib 0.5 mg and enzalutamide 160 mg once daily.
Glucocorticoids in CRPC
Glucocorticoids can induce a modest response and are an option in palliative care.
Abiraterone for M1 CRPC
Abiraterone is a CYP17 inhibitor and therefore inhibits testosterone biosynthesis. Abiraterone, also without olaparib, is approved for M1 CRPC both before and after docetaxel chemotherapy. The dosage is 1000 mg 1-0-0 p.o. combined with prednisolone 10 mg/d and standard androgen deprivation. After docetaxel chemotherapy, abiraterone prolonged survival in patients with M1 CRPC (14.8 vs. 10.9 months with placebo) (Bono et al., 2011). Before docetaxel chemotherapy, abiraterone prolonged progression-free survival (16.5 vs. 8.3 months) and overall survival (Ryan et al., 2013). Important adverse effects are hepatotoxicity, edema, hypokalemia, and hypertension caused by increased mineralocorticoid concentrations. Stop treatment if the disease progresses or treatment is not tolerated.
Enzalutamide for M0 and M1 CRPC
Enzalutamide is a modern androgen receptor antagonist and is approved for high-risk M0 CRPC and M1 CRPC both before and after docetaxel chemotherapy. The dosage is enzalutamide 160 mg (four 40 mg capsules) p.o. once daily combined with standard androgen deprivation. Prednisolone may be given but is not necessary. Phase III trials demonstrated significantly prolonged overall or progression-free survival with enzalutamide. Important adverse effects are hot flashes, diarrhea, headache, and, rarely, seizures. Stop treatment if the disease progresses or treatment is not tolerated.
Apalutamide for M0 CRPC
Apalutamide is a modern androgen receptor antagonist and is approved for high-risk M0 CRPC with a PSA doubling time below 10 months. The dosage is apalutamide 240 mg (four 60 mg capsules) p.o. once daily combined with standard androgen deprivation. In high-risk M0 CRPC, apalutamide prolonged median metastasis-free survival (41 vs. 16 months) (Smith et al., 2018a). Important adverse effects include skin rash. Stop treatment if the disease progresses or treatment is not tolerated.
Darolutamide for M0 CRPC
Darolutamide is a modern androgen receptor antagonist and is approved for high-risk M0 CRPC with a PSA doubling time below 10 months. The dosage is darolutamide 600 mg (two 300 mg tablets) p.o. in the morning and evening with meals, for a total daily dose of 1200 mg. Do not add prednisolone. In the pivotal ARAMIS trial, darolutamide combined with standard androgen deprivation prolonged metastasis-free survival (40 vs. 18 months with placebo and androgen deprivation); overall survival also showed a favorable trend (Fizazi et al., 2019).
Chemotherapy for CRPC
Chemotherapy offers only a moderate survival benefit in castration-resistant prostate cancer but may relieve pain in advanced disease. After treatment intensification with androgen receptor pathway inhibitors in the castration-sensitive stage, weigh chemotherapy sequentially against other treatment options in CRPC. Chemotherapy is particularly relevant in rapidly progressive or symptomatic disease, visceral metastases, ineligibility for 177Lu-PSMA, good performance status, or the absence of BRCA mutations. Docetaxel 75 mg/m2 every three weeks combined with prednisolone is the most effective regimen.
Second-Line Chemotherapy for CRPC
Cabazitaxel, a taxane, remains a treatment option for M1 CRPC after docetaxel, prior treatment with an androgen receptor pathway inhibitor, and no detected HRR mutation. In PSMA-positive disease, consider the sequence relative to 177Lu-PSMA. The dosage is cabazitaxel 25 mg/m2 IV every three weeks combined with prednisolone 10 mg/d.
Prevention of Osseous Complications in CRPC
30–50 % of patients with CRPC develop pathological fractures due to skeletal metastases. Regular administration of a bisphosphonate (zoledronic acid) or a RANK ligand inhibitor (denosumab) inhibits osteoclasts and reduces morbidity from bone metastases. Both drugs are recommended from the castration-resistant stage in patients with symptomatic bone metastases and an increased fracture risk.
Zoledronic acid:
Zoledronic acid reduced skeletal complications in phase III trials (33 vs. 44 %) (Saad et al., 2004). Renal adverse effects and osteonecrosis of the jaw (2–5 %) are serious complications. The dosage is zoledronic acid 4 mg IV every four weeks.
Denosumab:
Denosumab is a human monoclonal antibody that inhibits osteoclasts through interaction with RANKL and RANK. In a phase III trial, denosumab was superior to zoledronic acid: 20.7 vs. 17.1 months to the first skeletal complication. Denosumab is administered subcutaneously; the dosage is 120 mg every four weeks. The frequency of osteonecrosis of the jaw is comparable to that with zoledronic acid (Fizazi et al., 2011). For prevention of osteoporosis, administer denosumab 60 mg s.c. every six months.
Radiotherapy for painful bone metastases:
For a single or a few well-localized painful bone metastases, palliative external-beam radiotherapy is the treatment of choice. Standard regimens are 8 Gy in a single fraction, 20 Gy in five fractions, or 30 Gy in ten fractions.
Intravenous Radionuclides
223Ra (radium-223) is an established alpha emitter for patients with M1 CRPC, symptomatic bone metastases, and no visceral metastases. Radium-223 accumulates in areas of bone remodeling and can prolong survival and the time to skeletal complications (Parker et al., 2013). Because of the increased fracture risk, do not combine radium-223 with abiraterone; carefully weigh benefit against risk in patients with mildly symptomatic or asymptomatic bone metastases.
177Lu-PSMA ligands bind to PSMA-expressing prostate cancer cells and locally emit beta radiation. Sufficient PSMA expression on diagnostic PSMA-PET without relevant PSMA-negative tumor manifestations is required. In the VISION trial, 177Lu-PSMA-617 prolonged radiographic progression-free and overall survival in pretreated patients with PSMA-positive M1 CRPC (Sartor et al., 2021). This treatment is an important option after progression on androgen receptor pathway inhibitors and taxane chemotherapy. In the United States, the indication was expanded in 2025 to appropriate patients after ARPI treatment and before taxane chemotherapy. Common adverse effects are fatigue, nausea, xerostomia, myelosuppression, and worsening renal function.
Treatment of Hydronephrosis
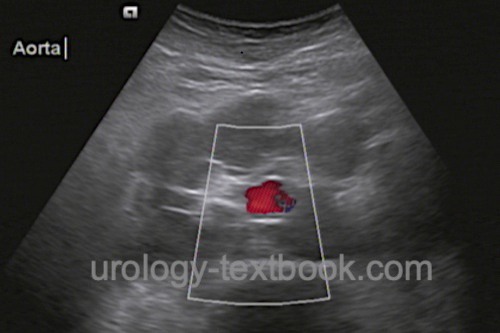
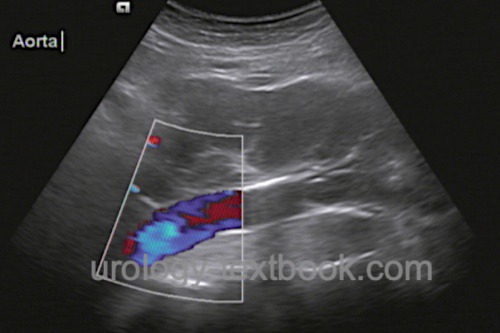
Local progression or lymph node metastases can cause obstructive uropathy of the upper urinary tract. Ureteral stents have a high failure rate in locally advanced prostate cancer with trigonal infiltration because of obstruction, infection, bleeding, and pain; percutaneous nephrostomy is then necessary.
 |
 |
Future Prospects for Treating CRPC
New treatment approaches for M1 CRPC increasingly focus on molecular selection, overcoming androgen receptor resistance, targeted radioligand therapy, and T-cell-mediated immunotherapies.
PARP inhibitors:
Rucaparib showed activity in the TRITON3 trial and is approved in the United States for BRCA-mutated mCRPC.
Cabozantinib and immune checkpoint inhibition:
Clinical trials have not yet demonstrated a survival benefit.
CDK4/6 inhibitors:
Cyclin-dependent kinase inhibitors, including ribociclib and abemaciclib, have not yet demonstrated a survival benefit when combined with chemotherapy or modern androgen deprivation therapy.
PI3K/AKT signaling pathway:
This is an important mechanism of castration resistance. Several agents targeting the PI3K/AKT signaling pathway, including ipatasertib and capivasertib, are in clinical development.
Androgen receptor signaling pathway:
Further androgen synthesis inhibitors and androgen receptor degraders are under development. BMS-986365 is being investigated in the phase III rechARge trial.
T-cell-mediated immunotherapies:
Several strategies targeting prostate cancer proteins are under investigation, including BiTEs (bispecific T-cell engagers) and CAR (chimeric antigen receptor) T cells. Xaluritamig, a STEAP1-directed T-cell engager, is being investigated in phase III trials for M1 CRPC.
Epigenetic treatment approaches:
The EZH2 inhibitor mevrometostat is being investigated in phase III trials combined with enzalutamide.
Other approaches:
Radioligands targeting PSMA or other targets and antibody-drug conjugates.
Follow-up Care
Follow-up After Curative Treatment
Follow-up evaluates treatment-related adverse effects (micturition, sexual function, ...) and measures the PSA concentration. Digital rectal examination is unnecessary after radical prostatectomy if the PSA concentration is unremarkable; after radiotherapy, its additional value is limited in the absence of a PSA increase. Perform imaging only if local recurrence or disease progression is suspected and if the findings would affect further treatment. For details on diagnosing and treating recurrence after radical prostatectomy or EBRT, see the respective sections above.
Follow-up intervals have not been prospectively validated. The EAU guidelines recommend follow-up three times during the first year (3, 6, and 12 months after treatment), every six months during the second and third years after treatment, and annually thereafter.
Follow-up During Androgen Deprivation Therapy
Three and six months after starting ADT, assess tolerability and clinical response, including symptoms and PSA values. Measuring the testosterone concentration is optional but mandatory in case of an inadequate response to treatment with GnRH agonists.
Plan further follow-up individually according to the risk of progression. In patients with M0 disease and a good response to ADT, PSA measurements and clinical examinations every 3–6 months are sufficient. Patients with clinical metastases require more frequent follow-up, including complete blood count, creatinine, liver enzymes, and alkaline phosphatase. Perform imaging individually according to symptoms and its clinical consequences.
Prevention
5α-Reductase Inhibitors
Long-term studies of 5α-reductase inhibitors for the treatment of BPH have shown a lower detection rate of prostate cancer in the active-treatment groups. The REDUCE trial demonstrated a reduced incidence with dutasteride. After four years of treatment with dutasteride 0.5 mg/d, the incidence in patients at increased risk was 20 % with dutasteride versus 25 % with placebo (Andriole et al., 2010). The effect of 5α-reductase inhibitors on prostate cancer-specific mortality remains unclear; pharmacological primary prevention is not recommended.
Selenium
Earlier prospective randomized and case-control studies partly reported preventive effects of selenium on prostate cancer development. However, the informative SELECT trial did not demonstrate a preventive effect; selenium supplementation for prostate cancer prevention is not recommended.
SELECT trial:
Selenium, vitamin E, selenium combined with vitamin E, or placebo (randomized, n=36 000 men): no differences between the active-treatment groups and placebo (Lippman et al., 2009).
Antioxidants
Both vitamin C and vitamin E have antioxidant properties that have been associated with a reduction in cancer risk. The randomized Physicians' Health Study II (n=14 600) found no protective effect of vitamin C or vitamin E (Gaziano et al., 2009). In the SELECT trial, vitamin E did not reduce the risk of prostate cancer. Vitamin C or vitamin E supplementation for prostate cancer prevention is not recommended.
Inhibition of Cyclooxygenase (COX)
Observational studies reported a lower risk of prostate cancer in patients with regular acetylsalicylic acid use. Because prospective prevention data are lacking and relevant adverse effects occur, COX inhibition is not recommended for prostate cancer prevention.
| Prostate cancer hormone treatment | Index | Prostate sarcoma |
Index: 1–9 A B C D E F G H I J K L M N O P Q R S T U V W X Y Z
References
EAU Guidelines EAU - EANM - ESTRO - ESUR - SIOG Guidelines on Prostate Cancer, https://uroweb.org/guidelines/prostate-cancer/.
Andriole, G. L.; Bostwick, D. G.; Brawley, O. W.;
Gomella, L. G.; Marberger, M.; Montorsi, F.; Pettaway, C. A.; Tammela, T.
L.; Teloken, C.; Tindall, D. J.; Somerville, M. C.; Wilson, T. H.; Fowler,
I. L.; Rittmaster, R. S. & Group, R. E. D. U. C. E. S.
Effect of
dutasteride on the risk of prostate cancer.
N Engl J Med, 2010,
362, 1192-1202
Beer, T. M.; Armstrong, A. J.; Rathkopf, D. E.; Loriot, Y.; Sternberg, C. N.; Higano, C. S.; Iversen, P.; Bhattacharya, S.; Carles, J.; Chowdhury, S.; Davis, I. D.; de Bono, J. S.; Evans, C. P.; Fizazi, K.; Joshua, A. M.; Kim, C.-S.; Kimura, G.; Mainwaring, P.; Mansbach, H.; Miller, K.; Noonberg, S. B.; Perabo, F.; Phung, D.; Saad, F.; Scher, H. I.; Taplin, M.-E.; Venner, P. M.; Tombal, B. und Investigators, P. R. E. V. A. I. L. Enzalutamide in metastatic prostate cancer before chemotherapy. N Engl J Med, 2014, 371, 424-433.
D. R. Berthold, G. R. Pond, F. Soban, R. de Wit, M. Eisenberger, and I. F.
Tannock.
Docetaxel plus prednisone or mitoxantrone plus prednisone for
advanced prostate cancer: updated survival in the tax 327 study.
J Clin Oncol, 26 (2): 242–245, Jan 2008.
URL https://dx.doi.org/10.1200/JCO.2007.12.4008.
K. N. Chi, et al., “Niraparib and Abiraterone Acetate for Metastatic Castration-Resistant Prostate Cancer.,” J Clin Oncol., vol. 41, no. 18, pp. 3339–3351, 2023.
De Bono, J. S.; Oudard, S.; Ozguroglu, M.; Hansen, S.;
Machiels, J.; Kocak, I.; Gravis, G.; Bodrogi, I.; Mackenzie, M. J.; Shen,
L.; Roessner, M.; Gupta, S.; Sartor, A. O. & Investigators, T. R. O. P. I.
C.
Prednisone plus cabazitaxel or mitoxantrone for metastatic
castration-resistant prostate cancer progressing after docetaxel
treatment: a randomised open-label trial.
Lancet, 2010,
376, 1147-1154
De Bono, J. S.; Logothetis, C. J.; Molina, A.; Fizazi,
K.; North, S.; Chu, L.; Chi, K. N.; Jones, R. J.; Goodman, O. B.; Saad,
F.; Staffurth, J. N.; Mainwaring, P.; Harland, S.; Flaig, T. W.; Hutson,
T. E.; Cheng, T.; Patterson, H.; Hainsworth, J. D.; Ryan, C. J.;
Sternberg, C. N.; Ellard, S. L.; Fléchon, A.; Saleh, M.; Scholz, M.;
Efstathiou, E.; Zivi, A.; Bianchini, D.; Loriot, Y.; Chieffo, N.; Kheoh,
T.; Haqq, C. M.; Scher, H. I. & Investigators, C. O. U. A.
Abiraterone
and increased survival in metastatic prostate cancer.
N Engl J Med, 2011,
364, 1995-2005
Finlay, I. G.; Mason, M. D. & Shelley, M.
Radioisotopes
for the palliation of metastatic bone cancer: a systematic review.
Lancet
Oncol, 2005, 6, 392-400.
Fizazi, K.; Carducci, M.; Smith, M.; Damião, R.; Brown,
J.; Karsh, L.; Milecki, P.; Shore, N.; Rader, M.; Wang, H.; Jiang, Q.;
Tadros, S.; Dansey, R. & Goessl, C.
Denosumab versus zoledronic
acid for treatment of bone metastases in men with castration-resistant
prostate cancer: a randomised, double-blind study.
Lancet, 2011,
377, 813-822
Gaziano, J. M.; Glynn, R. J.; Christen, W. G.; Kurth, T.; Belanger, C.; MacFadyen, J.; Bubes, V.; Manson, J. E.; Sesso, H. D. &
Buring, J. E.
Vitamins E and C in the prevention of prostate and total
cancer in men: the Physicians' Health Study II randomized controlled trial.
JAMA,
2009, 301, 52–62
Goldfarb u.a. 2006 GOLDFARB, C. R. ;
SRIVASTAVA, Neil C. ; GROTAS, Aaron B. ; ONGSENG,
Fukiat ; NAGLER, Harris M.:
Radionuclide imaging in urology.
In: Urol Clin North Am
33 (2006), Aug, Nr. 3, S. 319–328
Lippman, S. M.; Klein, E. A.; Goodman, P. J.; Lucia, M.
S.; Thompson, I. M.; Ford, L. G.; Parnes, H. L.; Minasian, L. M.; Gaziano,
J. M.; Hartline, J. A.; Parsons, J. K.; Bearden, J. D.; Crawford, E. D.;
Goodman, G. E.; Claudio, J.; Winquist, E.; Cook, E. D.; Karp, D. D.;
Walther, P.; Lieber, M. M.; Kristal, A. R.; Darke, A. K.; Arnold, K. B.;
Ganz, P. A.; Santella, R. M.; Albanes, D.; Taylor, P. R.; Probstfield, J.
L.; Jagpal, T. J.; Crowley, J. J.; Meyskens, F. L.; Baker, L. H. &
Coltman, C. A.
Effect of selenium and vitamin E on risk of prostate
cancer and other cancers: the Selenium and Vitamin E Cancer Prevention
Trial (SELECT).
JAMA, 2009, 301, 39–51
Kantoff, P. W.; Higano, C. S.; Shore, N. D.; Berger, E.
R.; Small, E. J.; Penson, D. F.; Redfern, C. H.; Ferrari, A. C.; Dreicer,
R.; Sims, R. B.; Xu, Y.; Frohlich, M. W.; Schellhammer, P. F. &
Investigators, I. M. P. A. C. T. S.
Sipuleucel-T immunotherapy for
castration-resistant prostate cancer.
N Engl J Med, 2010,
363, 411-422
Meyer u.a. 2005 MEYER, F. ; GALAN, P. ;
DOUVILLE, P. ; BAIRATI, I. ; KEGLE, P. ;
BERTRAIS, S. ; ESTAQUIO, C. ; HERCBERG, S.:
Antioxidant vitamin and mineral supplementation and prostate cancer
prevention in the SU.VI.MAX trial.
In: Int J Cancer
116 (2005), Nr. 2, S. 182–6
Miller, K.
[Castration resistant prostate cancer 2011].
Aktuelle Urol, 2011, 42, 95-102
Ryan, C. J.; Smith, M. R.; de Bono, J. S.; Molina, A.;
Logothetis, C. J.; de Souza, P.; Fizazi, K.; Mainwaring, P.; Piulats, J.
M.; Ng, S.; Carles, J.; Mulders, P. F. A.; Basch, E.; Small, E. J.; Saad,
F.; Schrijvers, D.; Poppel, H. V.; Mukherjee, S. D.; Suttmann, H.;
Gerritsen, W. R.; Flaig, T. W.; George, D. J.; Yu, E. Y.; Efstathiou, E.;
Pantuck, A.; Winquist, E.; Higano, C. S.; Taplin, M.; Park, Y.; Kheoh, T.;
Griffin, T.; Scher, H. I.; Rathkopf, D. E. & Investigators, C. O. U. A.
Abiraterone
in metastatic prostate cancer without previous chemotherapy.
N Engl
J Med, 2013, 368, 138-148.
Parker, C.; Nilsson, S.; Heinrich, D.; Helle, S. I.;
O'Sullivan, J. M.; Fosså, S. D.; Chodacki, A.; Wiechno, P.; Logue, J.;
Seke, M.; Widmark, A.; Johannessen, D. C.; Hoskin, P.; Bottomley, D.;
James, N. D.; Solberg, A.; Syndikus, I.; Kliment, J.; Wedel, S.; Boehmer,
S.; Dall'Oglio, M.; Franzén, L.; Coleman, R.; Vogelzang, N. J.;
O'Bryan-Tear, C. G.; Staudacher, K.; Garcia-Vargas, J.; Shan, M.; Bruland,
Ø. S.; Sartor, O. & Investigators, A. L. S. Y. M. P. C. A.
Alpha emitter radium-223 and survival in metastatic prostate cancer.
New Engl J Med 2013,
369, 213-223
O. Sartor et al., “Lutetium-177-PSMA-617 for Metastatic Castration-Resistant Prostate Cancer.,” NEJM, vol. 385, no. 12, pp. 1091–1103, 2021.
Leitlinienprogramm Onkologie (DGU, Deutsche Krebsgesellschaft, Deutsche Krebshilfe): Interdisziplinäre Leitlinie der Qualität S3 zur Früherkennung, Diagnose und Therapie der verschiedenen Stadien des Prostatakarzinoms https://www.leitlinienprogramm-onkologie.de/leitlinien/prostatakarzinom/
Wein, A. J.; Kavoussi, L. R.; Partin, A. P. & Peters, C. A.
Campbell-Walsh Urology
. Elsevier, 2015. ISBN 978-1455775675.
F. Saad et al., “PROpel: Phase III trial of olaparib (ola) and abiraterone (abi) versus placebo (pbo) and abi as first-line (1L) therapy for patients (pts) with metastatic castration-resistant prostate cancer (mCRPC).,” Journal of Clinical Oncology, vol. 40, no. 6suppl, p. 11, 2022.
Saad, F.; Gleason, D. M.; Murray, R.; Tchekmedyian, S.;
Venner, P.; Lacombe, L.; Chin, J. L.; Vinholes, J. J.; Goas, J. A. &
Zheng, M.
Long-term efficacy of zoledronic acid for the prevention of
skeletal complications in patients with metastatic hormone-refractory
prostate cancer
J Natl Cancer Inst, 2004, 96,
879-82
Scher, H. I.; Fizazi, K.; Saad, F.; Taplin, M.;
Sternberg, C. N.; Miller, K.; de Wit, R.; Mulders, P.; Chi, K. N.; Shore,
N. D.; Armstrong, A. J.; Flaig, T. W.; Fléchon, A.; Mainwaring, P.;
Fleming, M.; Hainsworth, J. D.; Hirmand, M.; Selby, B.; Seely, L.; de
Bono, J. S. & Investigators, A. F. F. I. R. M.
Increased survival
with enzalutamide in prostate cancer after chemotherapy.
N Engl J
Med, 2012, 367, 1187-1197.
 Deutsche Version: Prostatakarzinom
Urology-Textbook.com – Choose the Ad-Free, Professional Resource
This website is designed for physicians and medical professionals. It presents diseases of the genital organs through detailed text and images. Some content may not be suitable for children or sensitive readers. Many illustrations are available exclusively to Steady members. Are you a physician and interested in supporting this project? Join Steady to unlock full access to all images and enjoy an ad-free experience. Try it free for 7 days—no obligation.
New release: The first edition of the Urology Textbook as an e-book—ideal for offline reading and quick reference. With over 1300 pages and hundreds of illustrations, it’s the perfect companion for residents and medical students. After your 7-day trial has ended, you will receive a download link for your exclusive e-book.