You are here: Urology Textbook > Prostate > BPH > Treatment algorithm and drugs
Treatment Algorithm and Medication for Benign Prostatic Hyperplasia (BPH)
- Benign prostatic hyperplasia: definitions, epidemiology and etiology
- Benign prostatic hyperplasia: signs and symptoms
- Benign prostatic hyperplasia: diagnosis
- Benign prostatic hyperplasia: treatment algorithm
- Benign prostatic hyperplasia: surgical treatment
Treatment Options
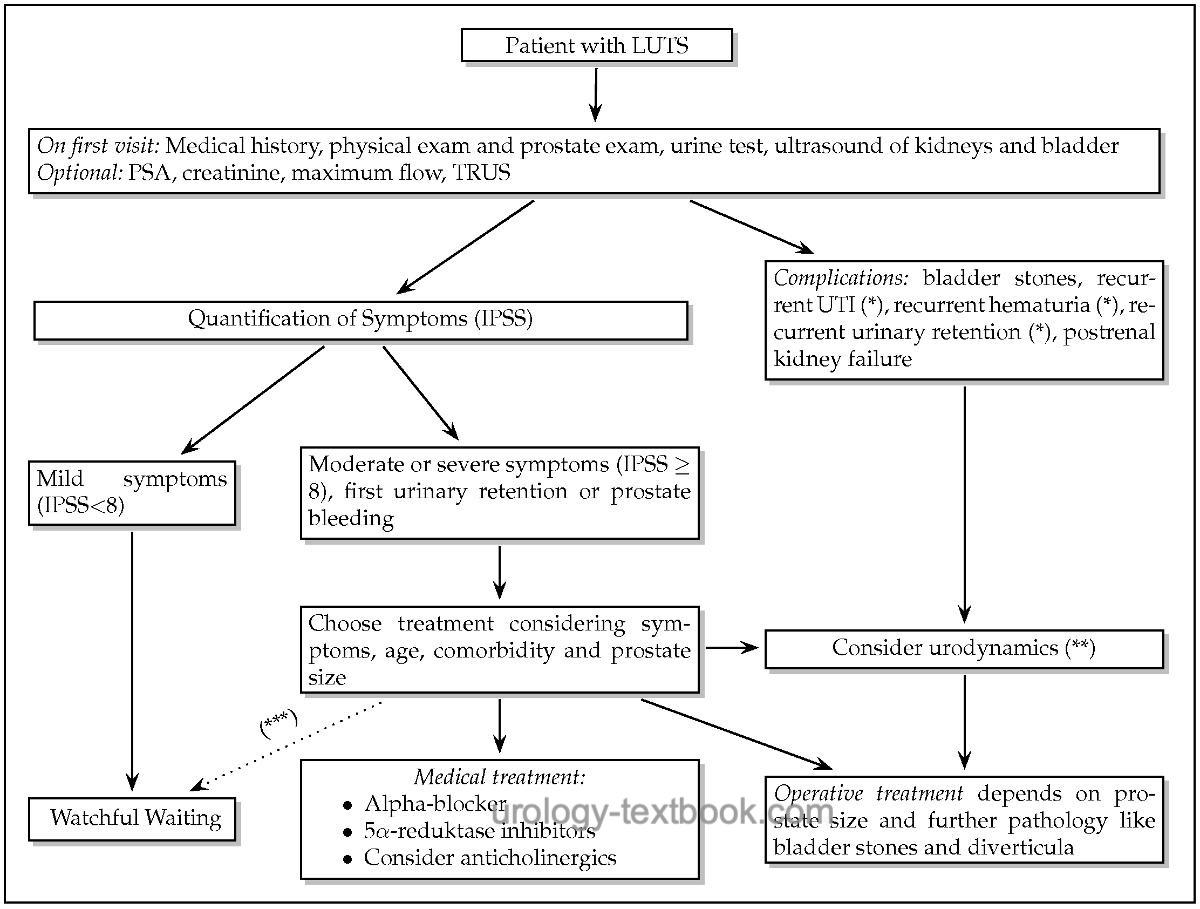
- Watchful waiting: Appropriate for mild symptoms without complications and without an immediate desire for treatment.
- Medical treatment: Indicated for bothersome moderate-to-severe LUTS without a mandatory indication for surgery. Treatment options include phytotherapeutic drugs, alpha-blockers, 5-alpha-reductase inhibitors, phosphodiesterase-5 inhibitors, antimuscarinics, and beta-3 agonists; some drugs may be combined.
- Invasive treatment: Indicated for inadequate efficacy or adverse effects of medical treatment, as well as for recurrent urinary retention, recurrent urinary tract infections, recurrent gross hematuria, bladder stones, postrenal renal insufficiency, and large bladder diverticula. The choice of procedure depends on prostate volume, the presence of a median lobe, anticoagulation, comorbidities, adverse-effect profile, and local expertise.
- Small prostate volume (below 40 ml): Transurethral incision of the prostate (TUIP), transurethral resection of the prostate (TURP), or laser vaporization.
- Intermediate prostate volume (40–100 ml): TURP, endoscopic enucleation of the prostate (EEP), or laser vaporization.
- Large prostate volume (> 75 ml): EEP or simple prostatectomy performed by an open, laparoscopic, or robot-assisted approach. If resection of a bladder diverticulum or removal of large bladder stones is required, simple prostatectomy may also be useful with smaller prostate volumes.
Algorithm for Initial Diagnosis and Treatment of Men with LUTS due to BPH
 |
Watchful Waiting in BPH
Watchful waiting is appropriate for patients with mild symptoms and no complications. It includes counseling, follow-up assessment, reduction of evening fluid intake, avoidance of alcohol and caffeine in patients with storage symptoms, treatment of constipation, and review of medication.
Symptoms improve spontaneously or remain stable in the long term in some patients. Risk factors for progression include a larger prostate volume (> 40 ml), a higher PSA concentration (> 3.2 ng/ml), a high IPSS, low maximum urinary flow, increasing residual urine, and older age.
Alpha-Blockers for Benign Prostatic Hyperplasia (BPH)
Alpha-blockers are the first-line drug class for benign prostatic syndrome. Numerous randomized trials have demonstrated the efficacy and safety of long-term treatment with the agents listed below. They improve symptoms rapidly, within days to weeks, but do not structurally reduce prostate size. Alpha-blockers are also administered to support a trial without catheter after urinary retention. See pharmacology and adverse effects of alpha-blockers.
Tamsulosin
Tamsulosin: 0.4 mg once daily. Dose titration is not required because of alpha1A selectivity. The OCAS (Oral Controlled Absorption System) formulation can be taken independently of meals.
Alfuzosin
Alfuzosin: Extended-release formulation, 5–10 mg once daily. Dose titration is not required.
Silodosin
Silodosin: A selective alpha-blocker with little effect on the cardiovascular system. Dose: 8 mg once daily; reduce to 4 mg in renal impairment.
Terazosin
Terazosin is a second-line drug because of its effect on arterial blood pressure, but it may be suitable for patients with arterial hypertension. Start with 1 mg orally in the evening, then increase weekly to 2–5–10 mg once daily in the evening, according to efficacy and tolerability.
Doxazosin
Doxazosin is a second-line drug because of its effect on arterial blood pressure, but it may be suitable for patients with arterial hypertension. Start with 1 mg orally in the evening, then increase weekly to 2–5–10 mg once daily in the evening, according to efficacy and tolerability.
Comparison of Alpha-Blockers
Alpha-blockers have broadly comparable effects on symptoms, but differ in their adverse-effect profiles, effects on blood pressure, and ejaculatory dysfunction. Terazosin and doxazosin more often cause dizziness, orthostatic hypotension, and fatigue. Tamsulosin and silodosin are receptor-selective (alpha1A) but more often cause ejaculatory dysfunction. Through tissue-specific accumulation, alfuzosin is functionally uroselective and is usually more favorable with respect to ejaculation.
BPH and Concomitant Arterial Hypertension
Alpha-blockers are not first-line treatment for arterial hypertension. In patients with both benign prostatic syndrome and hypertension, antihypertensive treatment should follow current guidelines; LUTS/BPS should preferably be treated with a uroselective alpha-blocker or another option.
5-Alpha-Reductase Inhibitors for Benign Prostatic Hyperplasia (BPH)
Dihydrotestosterone (DHT) mediates important androgen-dependent growth and differentiation signals in the prostate. 5-alpha-reductase inhibitors are indicated for moderate-to-severe LUTS/BPS with an enlarged prostate and a risk of progression, particularly when prostate volume is > 40 ml. They inhibit the intraprostatic conversion of testosterone to DHT. Finasteride predominantly inhibits type 2 5-alpha-reductase, whereas dutasteride inhibits types 1 and 2.
Their effect develops slowly and reaches a plateau after approximately 1–2 years; the achieved effect is maintained during continued treatment. The most important long-term benefits are symptom improvement and reductions in acute urinary retention and BPS-related surgery. The larger the prostate, the more pronounced the therapeutic effect. As the prostate shrinks, the PSA level decreases by up to 50 %; a baseline value before treatment is important for prostate cancer screening.
Pharmacokinetics and Adverse Effects of 5-Alpha-Reductase Inhibitors
Important adverse effects include decreased libido, erectile dysfunction, ejaculatory dysfunction, and, rarely, gynecomastia or depressive symptoms. In prevention trials, 5-alpha-reductase inhibitors reduced the overall incidence of prostate cancer but are not routinely recommended for prevention.
Dosage of 5-Alpha-Reductase Inhibitors
- Finasteride: 5 mg once daily orally.
- Dutasteride: 0.5 mg once daily orally.
Phosphodiesterase-5 Inhibitors for BPH
Smooth-muscle cells of the prostate, bladder, and blood vessels express phosphodiesterase 5. Phosphodiesterase-5 inhibitors enhance cGMP-mediated smooth-muscle relaxation. Tadalafil 5 mg once daily is approved for the treatment of male LUTS/BPS. It is particularly suitable for concomitant erectile dysfunction or intolerance of alpha-blockers.
The IPSS improves to a clinically relevant extent, whereas maximum urinary flow usually improves only slightly. Common adverse effects are headache, flushing, dyspepsia, back pain, and nasal congestion; nitrates are contraindicated.
Antimuscarinics for Benign Prostatic Hyperplasia (BPH)
Storage symptoms without relevant residual urine can be treated with antimuscarinics. They inhibit muscarinic receptors in the detrusor and reduce urgency, frequency, and urgency urinary incontinence. Significant obstruction or high residual urine increases the risk of urinary retention; monitoring of residual urine is appropriate.
Typical adverse effects are dry mouth, constipation, accommodation disorders, and cognitive adverse effects, particularly in older patients. In mixed storage and voiding symptoms, combination treatment with an alpha-blocker may be considered.
Beta-3 Agonists for Benign Prostatic Hyperplasia (BPH)
Beta-3 agonists such as mirabegron and vibegron are approved for treatment of overactive bladder. They may be considered in men with LUTS/BPS and predominant or persistent storage symptoms. Typical adverse effects are hypertension, tachycardia, headache, and urinary tract infections; caution is required in uncontrolled hypertension.
Beta-3 agonists do not inhibit detrusor contractility and do not increase the risk of urinary retention. In mixed storage and voiding symptoms, combination treatment with an alpha-blocker may be considered.
Treatment of Nocturia
Nocturia is a distressing symptom that may be caused or aggravated by BPS, nocturnal polyuria, sleep disorders, and numerous medical conditions; see nocturia. Cardiac, pulmonary, neurologic, nephrologic, metabolic, and medication-related causes should be assessed before specific treatment is initiated.
- Voiding diary: Used to diagnose nocturnal polyuria and bladder storage disorders.
- Behavioral treatment: Reduce evening fluid intake, avoid alcohol in the evening, adjust the timing of diuretic administration, and optimize sleep hygiene.
- Urologic treatment: Treat BPS in patients with voiding symptoms, relevant residual urine, or signs of obstruction; treat overactive bladder when storage symptoms predominate.
- Desmopressin: If nocturia persists despite the measures described above, desmopressin is an option: 50 µg before bedtime for men and 25 µg before bedtime for women (Han et al., 2017). Because of the risk of hyponatremia, sodium should be measured before treatment, after approximately 4–8 days, and after 1 month.
Drug Combination Treatment for Benign Prostatic Hyperplasia (BPH)
Combination treatment is appropriate when monotherapy does not adequately address the predominant symptom component or when an increased risk of progression is present.
- Alpha-blocker plus 5-alpha-reductase inhibitor: Standard combination for moderate-to-severe LUTS/BPS, enlarged prostate, and increased risk of progression. The alpha-blocker improves symptoms rapidly, whereas the 5-alpha-reductase inhibitor reduces prostate volume, the risk of urinary retention, and the need for surgery in the long term. Once stable symptom control has been achieved, the alpha-blocker can often be discontinued.
- Alpha-blocker plus antimuscarinic: An option for storage symptoms during alpha-blocker monotherapy. Use caution with high residual urine, after urinary retention, or with marked obstruction.
- Alpha-blocker plus beta-3 agonist: An option for storage symptoms during alpha-blocker monotherapy.
- Alpha-blocker plus 5-alpha-reductase inhibitor plus antimuscarinic or beta-3 agonist: Selective triple treatment for enlarged prostate with a risk of progression and persistent storage symptoms despite deobstructive treatment.
- Tadalafil plus 5-alpha-reductase inhibitor: An option for enlarged prostate with a risk of progression when early improvement of LUTS or treatment of concomitant erectile dysfunction is also desired.
- Tadalafil plus alpha-blocker: A selective option for persistent LUTS despite monotherapy or concomitant erectile dysfunction. Orthostatic hypotension, dizziness, and syncope may occur because of additive vasodilation.
Phytotherapeutic Drugs for Benign Prostatic Hyperplasia (BPH)
Single extracts or combinations of plant extracts from Sabal serrulata (dwarf palm), Serenoa repens (saw palmetto), Pygeum africanum (African plum), beta-sitosterol (found in many plants and oils), Secale cereale (rye), and other preparations are widely available. These preparations differ substantially in composition, extraction methods, and dosage. Evidence is heterogeneous; a reliable disease-modifying effect on prostate volume, urinary retention, or the risk of surgery has not been demonstrated.
| BPH diagnosis | Index | BPH Surgery |
Index: 1–9 A B C D E F G H I J K L M N O P Q R S T U V W X Y Z
References
Andriole u.a. 2004 ANDRIOLE, G. L. ;
ROEHRBORN, C. ; SCHULMAN, C. ; SLAWIN, K. M. ;
SOMERVILLE, M. ; RITTMASTER, R. S.:
Effect of dutasteride on the detection of prostate cancer in men with
benign prostatic hyperplasia.
In: Urology
64 (2004), Nr. 3, S. 537–41; discussion 542–3
Burnett und Wein 2006 BURNETT, A. L. ; WEIN,
A. J.:
Benign prostatic hyperplasia in primary care: what you need to know.
In: J Urol
175 (2006), Nr. 3 Pt 2, S. S19–24
Chapple 2004 CHAPPLE, C. R.:
Pharmacological therapy of benign prostatic hyperplasia/lower urinary
tract symptoms: an overview for the practising clinician.
In: BJU Int
94 (2004), Nr. 5, S. 738–44
DGU Guideline, “S2e Leitlinie Diagnostik und Therapie des Benignen Prostatasyndroms (BPS).,” 2023. [Online]. Available: https://register.awmf.org/assets/guidelines/043-034l_S2e_Diagnostik_Therapie_benignes_Prostatasyndrom_2023-04.pdf
Donovan u.a. 2000 DONOVAN, J. L. ; PETERS,
T. J. ; NEAL, D. E. ; BROOKES, S. T. ; GUJRAL,
S. ; CHACKO, K. N. ; WRIGHT, M. ; KENNEDY, L. G. ;
ABRAMS, P.:
A randomized trial comparing transurethral resection of the prostate,
laser therapy and conservative treatment of men with symptoms associated with
benign prostatic enlargement: The CLasP study.
In: J Urol
164 (2000), Nr. 1, S. 65–70
“EAU Guideline: Non-neurogenic Male LUTS,” Available: https://uroweb.org/guidelines/treatment-of-non-neurogenic-male-luts/.
Kopp, R. P.; Freedland, S. J. & Parsons, J. K.
Associations
of benign prostatic hyperplasia with prostate cancer: the debate continues.
Eur
Urol, 2011, 60, 699-700; discussion 701-2.
Ørsted, D. D.; Bojesen, S. E.; Nielsen, S. F. &
Nordestgaard, B. G.
Association of clinical benign prostate hyperplasia
with prostate cancer incidence and mortality revisited: a nationwide
cohort study of 3,009,258 men.
Eur Urol, 2011, 60,
691-698.
Parsons, J. Kellogg; Messer, Karen; White, Martha;
Barrett-Connor, Elizabeth; Bauer, Douglas C; Marshall, Lynn M; in Men
(MrOS) Research Group, Osteoporotic Fractures & the Urologic Diseases in
America Project
Obesity increases and physical activity decreases lower
urinary tract symptom risk in older men: the Osteoporotic Fractures in Men
study.
Eur Urol, 2011, 60, 1173-1180.
Reich u.a. 2006 REICH, O. ; GRATZKE, C. ;
STIEF, C. G.:
Techniques and long-term results of surgical procedures for BPH.
In: Eur Urol
49 (2006), Nr. 6, S. 970–8; discussion 978
Uygur u.a. 1998 UYGUR, M. C. ; GUR, E. ;
ARIK, A. I. ; ALTUG, U. ; EROL, D.:
Erectile dysfunction following treatments of benign prostatic
hyperplasia: a prospective study.
In: Andrologia
30 (1998), Nr. 1, S. 5–10
 Deutsche Version: Therapie der benignen Prostatahyperplasie
Urology-Textbook.com – Choose the Ad-Free, Professional Resource
This website is designed for physicians and medical professionals. It presents diseases of the genital organs through detailed text and images. Some content may not be suitable for children or sensitive readers. Many illustrations are available exclusively to Steady members. Are you a physician and interested in supporting this project? Join Steady to unlock full access to all images and enjoy an ad-free experience. Try it free for 7 days—no obligation.
New release: The first edition of the Urology Textbook as an e-book—ideal for offline reading and quick reference. With over 1300 pages and hundreds of illustrations, it’s the perfect companion for residents and medical students. After your 7-day trial has ended, you will receive a download link for your exclusive e-book.