You are here: Urology Textbook > Prostate > BPH > Symptoms
Benign Prostatic Hyperplasia: Signs and Symptoms
- Benign prostatic hyperplasia: definitions, epidemiology and etiology
- Benign prostatic hyperplasia: signs and symptoms
- Benign prostatic hyperplasia: diagnosis
- Benign prostatic hyperplasia: medical treatment
- Benign prostatic hyperplasia: surgical treatment
Lower Urinary Tract Symptoms of BPH
Storage Symptoms
Previously termed irritative symptoms. They occur during the storage phase and include frequency, nocturia, urgency, and urge, stress, or overflow urinary incontinence.
Causes
Postvoid residual urine causes the bladder to fill more rapidly and increases the risk of urinary tract infections. Detrusor hypertrophy increases bladder excitability. Cortical inhibition of bladder afferents and sphincter tone are less pronounced at night.
Voiding Symptoms
Previously termed obstructive symptoms. They occur during the voiding phase and include a weak or split urinary stream, hesitancy, straining to void, dysuria, intermittency, and urinary retention.
Causes
Static and dynamic obstruction of the prostatic urethra caused by BPH and increased smooth muscle tone.
Post-micturition Symptoms
Post-micturition symptoms occur after voiding and include a sensation of incomplete bladder emptying and post-micturition dribble.
Urinary Incontinence
Urinary incontinence is caused either by chronic urinary retention with overflow incontinence or by urge incontinence. Surgical treatment of benign prostatic syndrome may cause temporary or, rarely, persistent stress urinary incontinence.
Sexual Function
Severe LUTS impair sexual function, which may improve with effective treatment. 5-alpha reductase inhibitors can cause loss of libido and erectile dysfunction. Alpha-blockers and surgical treatment frequently cause retrograde ejaculation; erectile function is usually preserved.
Complications of Benign Prostatic Hyperplasia
Urinary Retention
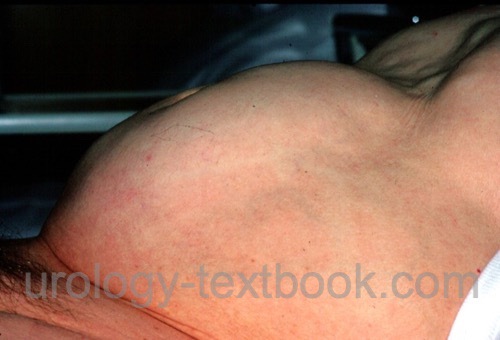
Risk factors for developing urinary retention are prostatitis, bladder overdistension, high fluid intake, alcohol, sexual activity, medication such as sympathomimetics and anticholinergics, bed rest, surgery, and general anesthesia. The prognosis after predictable urinary retention in the presence of risk factors is better than after spontaneous urinary retention in a patient with preexisting voiding symptoms and no identifiable trigger.
In indolent patients, urinary retention may present as a lower abdominal mass.
 |
Postrenal Kidney Failure
Hydronephrosis and postrenal kidney failure are often asymptomatic. Symptoms of uremia may occur in advanced kidney failure.
Further Complications
- Bladder diverticulum
- Gross hematuria
- Increased intra-abdominal pressure during voiding may cause hernias, hemorrhoids, or, rarely, micturition syncope.
- Pyelonephritis and sepsis.
- Bladder stones
Quantification of LUTS with the International Prostate Symptom Score
The International Prostate Symptom Score (IPSS) is essential for quantifying BPS symptoms and documenting treatment response. However, it has no specific diagnostic value because other conditions can also cause high IPSS values.
Evaluation of the IPSS
Add the scores for questions 1–7; the maximum total score is 35 points. Scores of 0–7 indicate mild symptoms, 8–19 moderate symptoms, and 20–35 severe symptoms. Question 8 evaluates quality of life and is reported separately from the total score.
1. Incomplete Emptying
How often have you had a sensation of not emptying your bladder completely after you finished urinating?
2. Frequency
How often have you had to urinate again less than two hours after you finished urinating?
3. Intermittency
How often have you found that you stopped and started again several times when you urinated?
4. Urgency
How often have you found it difficult to postpone urination?
5. Weak Stream
How often have you had a weak urinary stream?
6. Straining
How often have you had to push or strain to begin urination?
7. Nocturia
How many times did you most typically get up to urinate from the time you went to bed until you got up in the morning?
8. Quality of Life
How would you feel if you had to spend the rest of your life with your urinary condition the way it is now? The choices are delighted (0), pleased (1), mostly satisfied (2), mixed (3), mostly dissatisfied (4), unhappy (5), and terrible (6).
| BPH | Index | BPH diagnosis |
Index: 1–9 A B C D E F G H I J K L M N O P Q R S T U V W X Y Z
References
Andriole u.a. 2004 ANDRIOLE, G. L. ;
ROEHRBORN, C. ; SCHULMAN, C. ; SLAWIN, K. M. ;
SOMERVILLE, M. ; RITTMASTER, R. S.:
Effect of dutasteride on the detection of prostate cancer in men with
benign prostatic hyperplasia.
In: Urology
64 (2004), Nr. 3, S. 537–41; discussion 542–3
Burnett und Wein 2006 BURNETT, A. L. ; WEIN,
A. J.:
Benign prostatic hyperplasia in primary care: what you need to know.
In: J Urol
175 (2006), Nr. 3 Pt 2, S. S19–24
Chapple 2004 CHAPPLE, C. R.:
Pharmacological therapy of benign prostatic hyperplasia/lower urinary
tract symptoms: an overview for the practising clinician.
In: BJU Int
94 (2004), Nr. 5, S. 738–44
DGU Guideline, “S2e Leitlinie Diagnostik und Therapie des Benignen Prostatasyndroms (BPS).,” 2023. [Online]. Available: https://register.awmf.org/assets/guidelines/043-034l_S2e_Diagnostik_Therapie_benignes_Prostatasyndrom_2023-04.pdf
Donovan u.a. 2000 DONOVAN, J. L. ; PETERS,
T. J. ; NEAL, D. E. ; BROOKES, S. T. ; GUJRAL,
S. ; CHACKO, K. N. ; WRIGHT, M. ; KENNEDY, L. G. ;
ABRAMS, P.:
A randomized trial comparing transurethral resection of the prostate,
laser therapy and conservative treatment of men with symptoms associated with
benign prostatic enlargement: The CLasP study.
In: J Urol
164 (2000), Nr. 1, S. 65–70
“EAU Guideline: Non-neurogenic Male LUTS,” Available: https://uroweb.org/guidelines/treatment-of-non-neurogenic-male-luts/.
Kopp, R. P.; Freedland, S. J. & Parsons, J. K.
Associations
of benign prostatic hyperplasia with prostate cancer: the debate continues.
Eur
Urol, 2011, 60, 699-700; discussion 701-2.
Ørsted, D. D.; Bojesen, S. E.; Nielsen, S. F. &
Nordestgaard, B. G.
Association of clinical benign prostate hyperplasia
with prostate cancer incidence and mortality revisited: a nationwide
cohort study of 3,009,258 men.
Eur Urol, 2011, 60,
691-698.
Parsons, J. Kellogg; Messer, Karen; White, Martha;
Barrett-Connor, Elizabeth; Bauer, Douglas C; Marshall, Lynn M; in Men
(MrOS) Research Group, Osteoporotic Fractures & the Urologic Diseases in
America Project
Obesity increases and physical activity decreases lower
urinary tract symptom risk in older men: the Osteoporotic Fractures in Men
study.
Eur Urol, 2011, 60, 1173-1180.
Reich u.a. 2006 REICH, O. ; GRATZKE, C. ;
STIEF, C. G.:
Techniques and long-term results of surgical procedures for BPH.
In: Eur Urol
49 (2006), Nr. 6, S. 970–8; discussion 978
Uygur u.a. 1998 UYGUR, M. C. ; GUR, E. ;
ARIK, A. I. ; ALTUG, U. ; EROL, D.:
Erectile dysfunction following treatments of benign prostatic
hyperplasia: a prospective study.
In: Andrologia
30 (1998), Nr. 1, S. 5–10
 Deutsche Version: Symptome der benignen Prostatahyperplasie
Urology-Textbook.com – Choose the Ad-Free, Professional Resource
This website is designed for physicians and medical professionals. It presents diseases of the genital organs through detailed text and images. Some content may not be suitable for children or sensitive readers. Many illustrations are available exclusively to Steady members. Are you a physician and interested in supporting this project? Join Steady to unlock full access to all images and enjoy an ad-free experience. Try it free for 7 days—no obligation.
New release: The first edition of the Urology Textbook as an e-book—ideal for offline reading and quick reference. With over 1300 pages and hundreds of illustrations, it’s the perfect companion for residents and medical students. After your 7-day trial has ended, you will receive a download link for your exclusive e-book.