You are here: Urology Textbook > Prostate > Prostatitis > Acute bacterial prostatitis
Diagnosis and Treatment of Bacterial Prostatitis
Definition
Acute prostatitis is a bacterial infection of the prostate accompanied by fever and perineal pain (Benway and Moon, 2008). Prostatitis lasting three months or longer is considered chronic; see the definitions of prostatitis for the precise classification. See also the EAU Guidelines on Urological Infections.
Etiology
Intraprostatic Reflux
Urine and bacteria can reflux into the prostate, causing inflammation and the formation of prostatic calculi. Bacteria in the biofilm of prostatic calculi can persist despite adequate antibiotic therapy or the host immune response and sustain chronic infection.
Pathogens
Bacterial infection usually results from ascending spread through the urinary tract. The predominant pathogens are Escherichia coli and other Enterobacteriaceae, enterococci, and staphylococci. Neisseria gonorrhoeae and Chlamydia trachomatis should also be considered in sexually active men. Uncommon causes include Mycobacterium tuberculosis and BCG. Specific risk factors include intraprostatic reflux, phimosis, anal intercourse, urinary tract infection (acute cystitis or epididymitis), bladder catheterization, prostate biopsy, and transurethral resection, particularly in the presence of infected urine.
In persistent bacterial prostatitis, the less common causes listed above warrant greater consideration. Demonstrating an infection within the prostate is difficult because urethral contamination and nonpathogenic organisms in the prostate complicate diagnosis.
Pathology
Gross Pathology
Prostatic enlargement, hyperemia, edema, and sometimes abscesses.
Microscopic Pathology
Neutrophilic infiltration of acinar, periacinar, and stromal tissue, with microabscess formation.
Clinical Presentation
Systemic Symptoms
Fever and chills, and lumbar and perineal pain.
Voiding Symptoms
Urgency and urinary frequency, dysuria, and possibly obstructive symptoms ranging from a weak stream to urinary retention.
Rectal Examination
A brief, gentle digital rectal examination may reveal a markedly tender, enlarged, boggy prostate; an abscess may be palpable as fluctuation. Prostatic massage to obtain secretions is contraindicated in acute bacterial prostatitis.
Diagnosis
Urethral Swab
If sexually transmitted epididymitis is suspected, test for chlamydiae, mycoplasmas, and gonococci.
Urine Testing
Urine sediment shows pyuria, bacteriuria, and microscopic hematuria. Urine culture generally identifies the pathogen and must be obtained before treatment begins.
Microbiological Diagnosis of Chronic Prostatitis
Traditionally, four specimens were collected separately and examined by sediment microscopy and culture. Bacterial prostatitis is demonstrated by a tenfold increase in bacterial concentration in specimen 3 or 4:
- The first 10 mL of voided urine (urethral organisms).
- Midstream urine (bladder organisms).
- Expressed prostatic secretions (prostatic organisms): normally fewer than 10 leukocytes per high-power field.
- The first 10 mL of urine after prostatic massage (prostatic organisms).
Because of the time and cost involved, the two-glass test has become established; recent studies have confirmed its equivalence:
- Midstream urine (bladder organisms).
- The first 10 mL of urine after prostatic massage (prostatic organisms).
Laboratory Tests
Leukocytosis with a left shift, elevated C-reactive protein, and elevated prostate-specific antigen as evidence of inflammatory involvement of the prostate. Blood cultures may identify the pathogen in patients with high fever or clinical signs of urosepsis.
Bladder and Prostate Ultrasonography
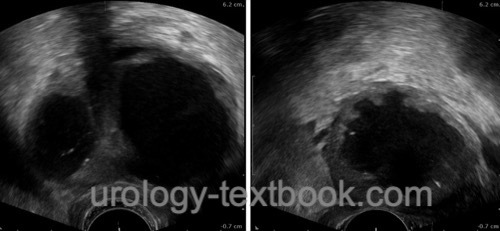
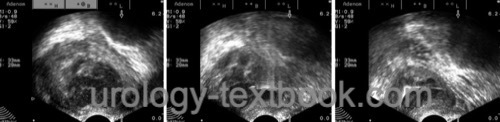
Transabdominal assessment of postvoid residual urine, bladder wall, and intravesical abnormalities such as stones. Assess prostate size and look for a prostatic abscess.
Transrectal Ultrasonography
Transrectal ultrasonography is indicated when an abscess is suspected, the disease is severe, or the clinical response to antibiotics is inadequate. CT or MRI can be used instead.
Treatment
Empiric Antibiotic Therapy
Begin treatment while awaiting microbiological results. Selection depends on severity, local resistance patterns, prior antibiotics, risk factors for multidrug-resistant organisms, and suspicion of sexually transmitted pathogens. Fluoroquinolones have high antibacterial activity and good tissue penetration even when given orally: for example, ofloxacin 200–400 mg twice daily by mouth or ciprofloxacin 500 mg twice daily by mouth. If sexual transmission is suspected, start doxycycline 100 mg twice daily by mouth.
Severe disease requires inpatient intravenous therapy. Options include piperacillin/tazobactam 4.5 g three times daily or a second-, third-, or fourth-generation cephalosporin, such as cefuroxime 1.5 g every 12 hours, ceftriaxone 1–2 g every 24 hours, or cefotaxime 1–2 g every 12 hours intravenously. Carbapenems are indicated for urosepsis or suspected multidrug-resistant gram-negative pathogens. After clinical stabilization and receipt of susceptibility results, treatment can be narrowed and switched to an appropriate oral agent.
Duration of Antibiotic Therapy
Continue parenteral treatment until clinical stabilization, usually for 3–7 days, then switch to a suitable oral antibiotic at full dose for 2–4 weeks.
Sexually Transmitted Prostatitis
For nongonococcal infection, doxycycline 100 mg twice daily by mouth for 10 days is recommended. If gonorrhea is possible, also administer ceftriaxone 1–2 g parenterally as a single dose.
Supportive Care
An indwelling suprapubic catheter for postvoid residual urine or fever refractory to treatment; bed rest; rehydration; anti-inflammatory drugs for fever and pain (e.g., diclofenac or metamizole); and macrogol to soften the stool.
Prostatic Abscess
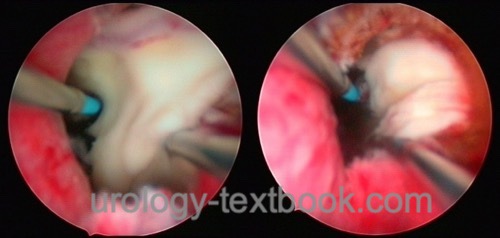
Depending on extent, treat with a single transperineal needle aspiration or place a transperineal drain (9–12 Fr pigtail catheter) under transrectal ultrasound guidance. Send aspirated material for microbiological testing. Centrally located abscesses can alternatively be drained by transurethral resection.
Chronic Bacterial Prostatitis
Antibiotic therapy for 4–6 weeks, selected according to culture results.
Gram-Negative Bacteria
Fosfomycin 3 g every three days (off-label), or a fluoroquinolone such as ofloxacin 200–400 mg twice daily or ciprofloxacin 250–500 mg twice daily.
Chlamydia trachomatis
Azithromycin for four weeks (1 g every seven days) or doxycycline 100 mg twice daily for 28 days.
Mycoplasma genitalium
Resistance is common; ideally, test for macrolide resistance mutations at diagnosis to guide selection of an appropriate antibiotic, such as azithromycin or a fluoroquinolone.
Lack of Improvement or Recurrence
If symptoms do not improve, reassess the differential diagnosis of chronic pelvic pain syndrome (CPPS). Consider low-dose, long-term antibiotic prophylaxis for recurrence only cautiously and after an individualized assessment of benefits and risks. Transurethral resection can be discussed in selected refractory cases; controlled studies are lacking. Acute or chronic bacterial prostatitis can trigger CPPS.
| Prostatitis Definitionen | Index | Chronic pelvic pain syndrome |
Index: 1–9 A B C D E F G H I J K L M N O P Q R S T U V W X Y Z
References
Benway, B. M. & Moon, T. D.
Bacterial prostatitis.
Urol Clin North Am, 2008, 35, 23-32;
G. Bonkat, R. Bartoletti, F. Bruyère, S. E. Geerlings, F. Wagenlehner, and B. Wullt, “EAU Guideline: Urological Infections.” [Online]. Available: https://uroweb.org/guidelines/urological-infections/
Krieger u.a. 1999 KRIEGER, J. N. ; NYBERG,
Jr. ; NICKEL, J. C.:
NIH consensus definition and classification of prostatitis.
In: Jama
282 (1999), Nr. 3, S. 236–7
Nickel 2003 NICKEL, J. C.:
Recommendations for the evaluation of patients with prostatitis.
In: World J Urol
21 (2003), Nr. 2, S. 75–81
 Deutsche Version: Akute bakterielle Prostatitis
Urology-Textbook.com – Choose the Ad-Free, Professional Resource
This website is designed for physicians and medical professionals. It presents diseases of the genital organs through detailed text and images. Some content may not be suitable for children or sensitive readers. Many illustrations are available exclusively to Steady members. Are you a physician and interested in supporting this project? Join Steady to unlock full access to all images and enjoy an ad-free experience. Try it free for 7 days—no obligation.
New release: The first edition of the Urology Textbook as an e-book—ideal for offline reading and quick reference. With over 1300 pages and hundreds of illustrations, it’s the perfect companion for residents and medical students. After your 7-day trial has ended, you will receive a download link for your exclusive e-book.