You are here: Urology Textbook > Kidneys > Renal abscess
Renal Abscess: Symptoms, Diagnosis and Treatment
Review literature: (Angel et al., 2003) (Shu et al., 2004).
Definition of a Renal Abscess
A renal abscess is a collection of pus within the renal capsule. The infection may extend into the retroperitoneum. It was historically called a renal carbuncle.
Etiology of Renal Abscess
Ascending Infection:
Renal abscesses most commonly develop as a complication of an ascending urinary tract infection. Predisposing factors include urinary tract obstruction, nephrolithiasis, vesicoureteral reflux, diabetes mellitus, immunosuppression, and structural abnormalities of the urinary tract. The most common pathogen is Escherichia coli, followed by Klebsiella pneumoniae, Proteus mirabilis, and other Enterobacterales. After urologic procedures or with catheter-associated infection, Pseudomonas aeruginosa and gram-positive pathogens such as Enterococcus should also be considered.
Hematogenous Infection with Staphylococci:
Before the antibiotic era, hematogenously disseminated gram-positive staphylococci were the leading cause of renal abscesses. Current risk groups include people who inject drugs, patients receiving dialysis, patients in intensive care, and patients with valvular heart disease or endocarditis.
Signs and Symptoms of a Renal Abscess
Fever, chills, flank pain, and malaise are common. Flank swelling and redness are uncommon [fig. renal abscess]. Advanced disease may cause signs of sepsis. Subacute presentations with weight loss are also possible.
Renal Abscess: Diagnostic Workup
Urine and Blood Cultures:
Obtain urine and blood cultures before starting antibiotic therapy.
Laboratory Tests:
Obtain a complete blood count, coagulation studies (PTT, PT), CRP, liver enzymes, and kidney function tests. If sepsis is suspected, obtain blood cultures and blood gas analysis and measure procalcitonin.
Ultrasonography:
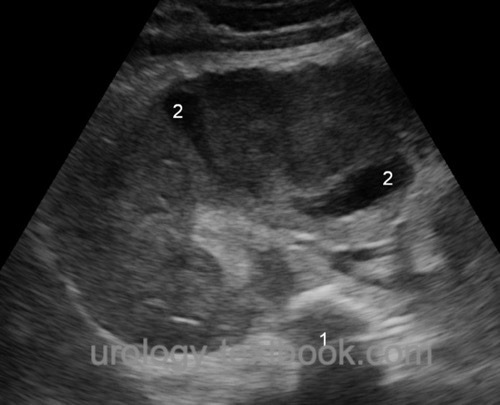
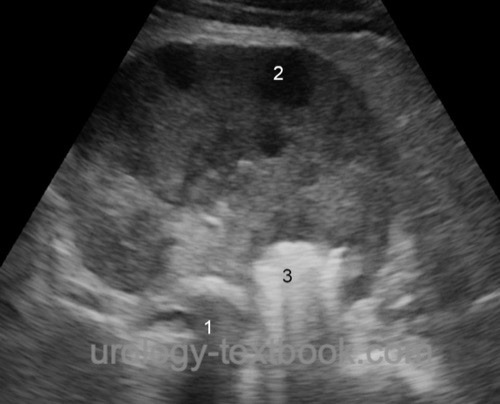
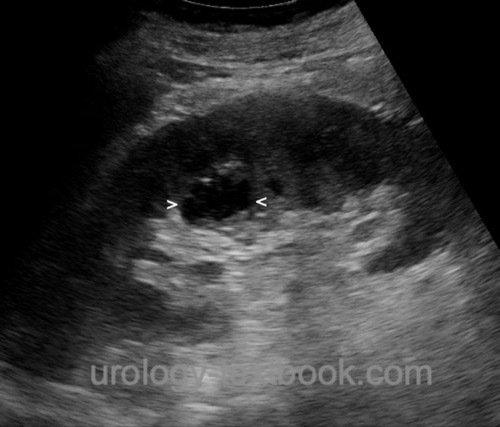
A hypoechoic mass within the renal capsule is a sonographic sign of renal abscess. Markedly echogenic structures suggest air within the abscess (echogenic echoes with posterior acoustic shadowing). Doppler sonography may show increased blood flow at the abscess margin, whereas blood flow is often absent in the center. Obtain a CT scan if the ultrasound findings are abnormal.
 |
 |
 |
Computed Tomography:
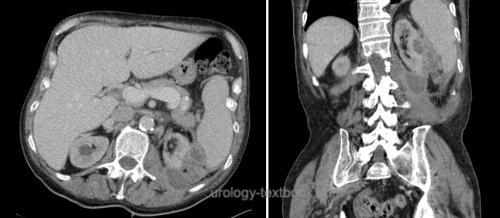
CT is the imaging modality of choice when renal abscess is suspected. If a patient does not improve with treatment for pyelonephritis within 48–72 hours, or deteriorates clinically, obtain CT imaging promptly. On noncontrast CT, the kidney may be enlarged and the abscess appears as a hypodense area. Air inclusions are possible. After administration of contrast medium, enhancement of the perfused abscess margin produces a ring-like appearance.
 |
MRI:
Use MRI when CT is contraindicated.
Intravenous Urography:
Intravenous urography is a historical, obsolete examination. If renal abscess is suspected, obtain CT imaging. Possible findings on urography include delayed contrast excretion, an enlarged renal shadow, and displacement of the collecting system by the inflammatory mass.
Differential Diagnosis:
Consider acute pyelonephritis without abscess formation, acute focal bacterial nephritis (lobar nephronia), perinephric abscess, xanthogranulomatous pyelonephritis, infected renal cyst, necrosis or liquefaction of a renal tumor, and renal infarction. In an unexplained septic presentation, perform a systematic search for the source.
Treatment of a Renal Abscess
Intravenous Antibiotic Therapy:
Empiric therapy should cover Enterobacterales and be guided by disease severity, risk factors, local resistance patterns, kidney function, and possible sepsis. Options include piperacillin and tazobactam 4.5 g 1-1-1 IV or a third- or fourth-generation cephalosporin, e.g., ceftriaxone 1–2 g every 24 hours or cefotaxime 1–2 g every 12 hours IV. Carbapenems are indicated for urosepsis or suspected multidrug-resistant gram-negative pathogens. After clinical stabilization and receipt of susceptibility results, therapy may be de-escalated to an appropriate oral antibiotic. See also the section on antibiotic therapy for pyelonephritis.
Percutaneous Drainage:
In addition to intravenous antibiotic therapy, abscesses larger than 3 cm should be aspirated and drained percutaneously. Send the aspirate for microbiological testing. Abscesses larger than 5 cm may require multiple drainages.
Follow-up:
Repeat CT if fever persists or laboratory findings fail to improve.
Surgery:
Surgical treatment, including nephrectomy, is indicated if the patient does not improve despite adequate drainage and antibiotic therapy, particularly when the kidney is destroyed and nonfunctional.
| Chronic pyelonephritis | Index | Perinephric abscess |
Index: 1–9 A B C D E F G H I J K L M N O P Q R S T U V W X Y Z
References
Angel u.a. 2003 ANGEL, C. ; SHU, T. ; GREEN, J. ; ORIHUELA, E. ; RODRIQUEZ, G. ; HENDRICK, E.: Renal and peri-renal abscesses in children: proposed physio-pathologic mechanisms and treatment algorithm.In: Pediatr Surg Int
19 (2003), Nr. 1–2, S. 35–9
Shu u.a. 2004 SHU, T. ; GREEN, J. M. ;
ORIHUELA, E.:
Renal and perirenal abscesses in patients with otherwise anatomically
normal urinary tracts.
In: J Urol
172 (2004), Nr. 1, S. 148–50
 Deutsche Version: Nierenabszess
Urology-Textbook.com – Choose the Ad-Free, Professional Resource
This website is designed for physicians and medical professionals. It presents diseases of the genital organs through detailed text and images. Some content may not be suitable for children or sensitive readers. Many illustrations are available exclusively to Steady members. Are you a physician and interested in supporting this project? Join Steady to unlock full access to all images and enjoy an ad-free experience. Try it free for 7 days—no obligation.
New release: The first edition of the Urology Textbook as an e-book—ideal for offline reading and quick reference. With over 1300 pages and hundreds of illustrations, it’s the perfect companion for residents and medical students. After your 7-day trial has ended, you will receive a download link for your exclusive e-book.