You are here: Urology Textbook > Ureters > Retroperitoneal fibrosis
Retroperitoneal Fibrosis: Diagnosis and Treatment of Ormond Disease
Definition of Retroperitoneal Fibrosis
Retroperitoneal fibrosis is a fibroinflammatory disease of the retroperitoneum characterized by encasement of retroperitoneal structures, particularly the aorta, iliac vessels, and ureters. It frequently causes ureteral obstruction, hydronephrosis, and loss of renal function (Vaglio and Maritati, 2016).
 |
Epidemiology of Retroperitoneal Fibrosis
The male-to-female ratio is 2:1. The prevalence is 1–2/100,000, and the age of onset is 40–60 years.
Causes (Etiology) of Retroperitoneal Fibrosis
Idiopathic and IgG4-associated forms:
In most patients, no clear secondary cause is identified. A substantial proportion of cases previously classified as idiopathic fall within the spectrum of IgG4-related disease. Autoimmune mechanisms, chronic periaortitis, and fibroinflammatory reactions have been proposed.
Known triggers
Drugs: Ergot alkaloids and dopamine agonists are the classic agents described. Evidence for other drugs, including beta blockers, analgesics, haloperidol, and other substances, is inconsistent.
Infectious and inflammatory diseases:
Tuberculosis, chronic infections, inflammatory bowel disease, sarcoidosis, and systemic autoimmune diseases.
Fibrotic and IgG4-related diseases:
Associated conditions include sclerosing mediastinitis, sclerosing cholangitis, orbital pseudotumor, and Riedel thyroiditis. Rare associations with systemic lupus erythematosus or juvenile idiopathic arthritis occur in children.
Other triggers:
Radiation, retroperitoneal hemorrhage, pelvic surgery, trauma, and malignancy.
Pathology of Retroperitoneal Fibrosis
A firm mass of connective tissue surrounds the large retroperitoneal vessels and may also encase and infiltrate the ureters. It typically extends craniocaudally from the renal hilum to the sacral promontory. Active inflammatory changes in the connective tissue at the edge of the fibrotic mass include lymphocytes, plasma cells, and histiocytes. The tissue in the center is more collagenized and less inflamed.
Signs and Symptoms
- Flank pain is constant and dull, begins in the flanks, and radiates to the lower abdomen.
- Nonspecific symptoms such as weight loss, malaise, nausea, and vomiting may occur at the beginning of the inflammatory process. Lymphadenopathy is generally absent.
- Advanced ureteral obstruction may cause hydronephrosis, recurrent urinary tract infections, oliguria, anuria, or renal insufficiency.
Diagnostic Workup of Retroperitoneal Fibrosis
Laboratory tests:
The erythrocyte sedimentation rate (ESR) and CRP are elevated. The workup should also include urinalysis, creatinine, electrolytes, a differential blood count, autoantibodies (ANA, ANCA), immunoglobulins including IgG4, and rheumatoid factor. In men, measure PSA, AFP, β-hCG, and LDH.
Ultrasound imaging:
Ultrasound reliably identifies hydronephrosis and allows follow-up. The retroperitoneal connective tissue mass around the aorta may also be visualized when acoustic windows are adequate.
CT or MRI of the abdomen:
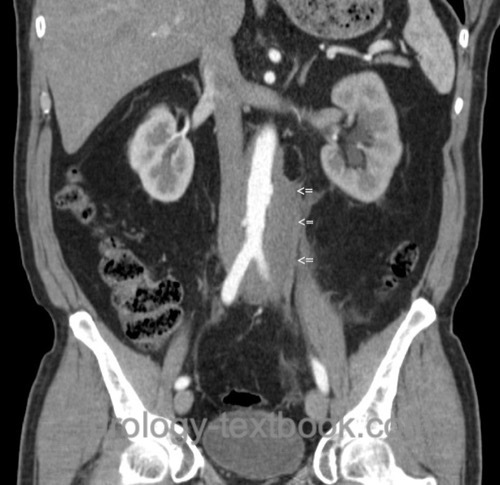
Abdominal imaging shows a mantle-shaped soft-tissue mass surrounding the aorta, iliac vessels, and ureters [CT image]. Contrast enhancement and restricted diffusion may indicate inflammatory activity. Bilateral hydronephrosis may also be present.
Urography:
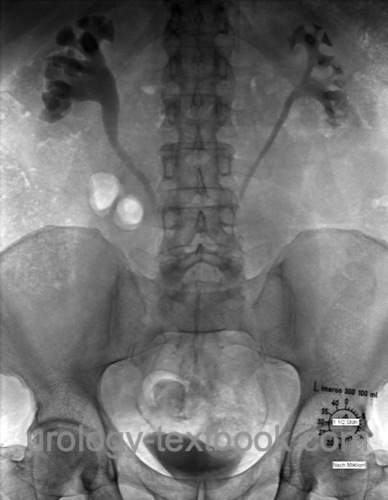
Intravenous urography should be performed only if cross-sectional imaging is unavailable. Typical findings include bilateral hydronephrosis and medial displacement of the proximal and mid ureters [image].
 |
Retrograde pyelography:
Retrograde pyelography is indicated when retrograde urinary drainage is planned, when ureteral anatomy is unclear, or before endoscopic treatment. It shows the location and length of the obstruction and helps exclude an intrinsic ureteral obstruction.
Renal scintigraphy:
Renal scintigraphy determines split renal function and quantifies urinary drainage obstruction.
Percutaneous biopsy:
Biopsy of the retroperitoneal mass is used to exclude malignancy, particularly in cases of atypical disease extent, a nodular mass, marked lymphadenopathy, a history of malignancy, absence of inflammatory activity, or failure to respond to glucocorticoids. When the clinical and imaging findings are typical, treatment may reasonably be started without biopsy.
Differential Diagnosis of Retroperitoneal Fibrosis
The main differential diagnoses are lymphoma, retroperitoneal metastases, sarcoma, retroperitoneal germ cell tumor, ureteral urothelial carcinoma, multiple myeloma, pancreatic cancer, tuberculosis, abscess, and Erdheim-Chester disease.
Erdheim-Chester disease:
A rare histiocytosis that typically affects the long bones and often involves the retroperitoneum, perirenal space, or periureteral tissues. CT may show the characteristic hairy kidney sign: streak-like perirenal infiltrates that encase the kidneys. Ureteral stenting is necessary when obstruction is present. Treatment with signal transduction inhibitors, such as BRAF or MEK inhibitors, is possible.
Treatment of Retroperitoneal Fibrosis
Acute renal decompression
Initial urinary drainage with a double-J (DJ) ureteral stent or, less commonly, a percutaneous nephrostomy is generally necessary in patients with significant ureteral obstruction, worsening renal function, infection, a solitary kidney, or pain.
Medical treatment
Prednisolone is the first-line drug treatment for active idiopathic or IgG4-associated retroperitoneal fibrosis. One possible regimen is prednisolone 0.75–1 mg/kg/day, up to a maximum of 60–80 mg/day, for 4 weeks. The dose is then reduced by 10 mg every 2–4 weeks to 20 mg/day, followed by a slower reduction of 2.5–5 mg every 2–4 weeks to 5–7.5 mg/day. Treatment often lasts 6–12 months and is guided by symptoms, inflammatory markers, imaging, urinary drainage, and renal function. Azathioprine, mycophenolate mofetil, methotrexate, or rituximab may be considered for relapse, glucocorticoid dependence, or contraindications.
Secondary retroperitoneal fibrosis
Discontinue causative drugs and treat secondary causes, such as malignancy, infection, radiation effects, or systemic autoimmune disease.
Surgical treatment
Ureterolysis with intraperitoneal transposition of the ureters is indicated for persistent ureteral obstruction despite adequate medical treatment, intolerance of long-term stenting, or a diagnosis that remains unclear after biopsy. Surgery requires salvageable renal function on the affected side. Nonfunctioning kidneys should undergo nephrectomy only when symptoms, infection, or complications occur.
Technique of ureterolysis:
The standard procedure is open ureterolysis with biopsy, mobilization of the ureters, and intraperitonealization or omental interposition. In experienced centers, a laparoscopic or robot-assisted approach may also be used when the anatomy is suitable.
Ureteral replacement:
Depending on the disease manifestations and ureteral involvement, segmental or complete ureteral replacement may be necessary. Options include a Boari flap, bowel segment interposition, or autologous kidney transplantation; see the section on ureteral stricture.
Follow-up
Retroperitoneal fibrosis is a chronic relapsing disease and requires long-term follow-up. Monitoring includes symptoms, blood pressure, creatinine, urinalysis, ESR/CRP, and ultrasound assessment of hydronephrosis. CT or MRI is used initially to assess treatment response and later if recurrence is suspected or every 1–2 years after immunosuppression is discontinued.
| Ureter, anatomy | Index | Ureter, diseases |
Index: 1–9 A B C D E F G H I J K L M N O P Q R S T U V W X Y Z
References
Vaglio A, Maritati F. Idiopathic retroperitoneal fibrosis. J Am Soc Nephrol. 2016;27(7):1880–1889. doi:10.1681/ASN.2015101110.
 Deutsche Version: Morbus Ormond: retroperitoneale Fibrose
Urology-Textbook.com – Choose the Ad-Free, Professional Resource
This website is designed for physicians and medical professionals. It presents diseases of the genital organs through detailed text and images. Some content may not be suitable for children or sensitive readers. Many illustrations are available exclusively to Steady members. Are you a physician and interested in supporting this project? Join Steady to unlock full access to all images and enjoy an ad-free experience. Try it free for 7 days—no obligation.
New release: The first edition of the Urology Textbook as an e-book—ideal for offline reading and quick reference. With over 1300 pages and hundreds of illustrations, it’s the perfect companion for residents and medical students. After your 7-day trial has ended, you will receive a download link for your exclusive e-book.