You are here: Urology Textbook > Prostate > BPH > Surgical treatment
Surgery for Benign Prostatic Hyperplasia (BPH)
- Benign prostatic hyperplasia: definitions, epidemiology and etiology
- Benign prostatic hyperplasia: signs and symptoms
- Benign prostatic hyperplasia: diagnosis
- Benign prostatic hyperplasia: medical treatment
- Benign prostatic hyperplasia: surgical treatment
Transurethral Resection of the Prostate (TURP)
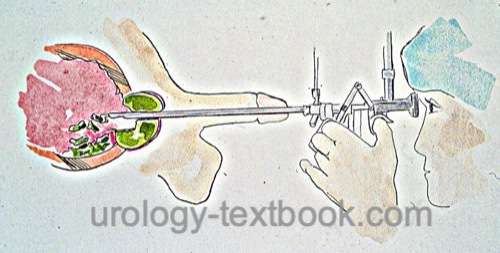
Transurethral resection of the prostate (TURP) is the endoscopic removal of obstructing prostate tissue with an electrical loop. TURP is one of the most frequently used reference procedures for invasive treatment of benign prostatic syndrome, particularly for small and intermediate prostate volumes.
 |
Indication
The most common indication for TURP is moderate-to-severe symptoms of benign prostatic syndrome despite medical treatment. Surgery is also indicated for:
- Recurrent urinary retention.
- Recurrent urinary tract infections.
- Recurrent gross hematuria.
- Bladder stones.
- Postrenal renal insufficiency.
- Large bladder diverticula.
Technique and Complications
See transurethral resection of the prostate.
Results
TURP provides marked and durable improvement in urinary flow, IPSS, quality of life, and residual urine volume. Voiding symptoms respond better than storage symptoms. Nocturia and urgency may persist, particularly in the presence of detrusor overactivity, nocturnal polyuria, or medical causes.
Transurethral Incision of the Prostate (TUIP)
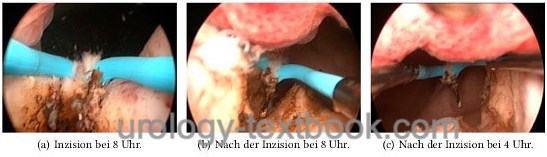
Transurethral incision of the prostate (TUIP) relieves obstruction by incising the bladder neck and prostate tissue.
Indication
TUIP is suitable for a small prostate, usually < 30 ml, without a relevant median lobe. Its advantages are lower surgical morbidity and a lower rate of retrograde ejaculation than TURP.
Technique
Using a resectoscope and a dedicated hook electrode, incisions are made from the bladder neck to the verumontanum bilaterally at the 4 and 8 o'clock positions.
 |
Endoscopic Enucleation of the Prostate (EEP)
In anatomical endoscopic enucleation of the prostate (AEEP/EEP), the prostate adenoma is mobilized transurethrally in the dissection plane between the adenoma and peripheral prostate, followed by morcellation or resection.
Indication
EEP is an alternative to TURP and to open or minimally invasive simple prostatectomy. With adequate expertise, any prostate volume can be treated effectively.
Technique and Complications
Different energy sources may be used for tissue division:
- HoLEP: Holmium laser enucleation of the prostate.
- ThuLEP: Thulium laser enucleation of the prostate.
- GreenLEP: GreenLight laser enucleation of the prostate.
- BipolEP: Bipolar enucleation of the prostate.
Results and Complications
Randomized trials show comparable or superior functional efficacy compared with TURP or simple prostatectomy, with shorter catheterization time, less blood loss, and shorter hospital stay. The risk of TUR syndrome is very low with isotonic irrigation.
Disadvantages
Disadvantages include a relevant learning curve, equipment and fiber costs, and an increased risk of usually transient postoperative stress urinary incontinence.
Transurethral Laser Procedures for Benign Prostatic Syndrome
Technique
Various laser sources with different physical properties enable coagulation, vaporization, vaporesection, or enucleation of prostate tissue.
Transurethral Ultrasound-Guided Laser-Induced Prostatectomy (TULIP)
TULIP is a historical procedure that is no longer used because direct visualization of the laser effect was not possible.
Visual Laser Ablation of the Prostate (VLAP)
VLAP is a historical side-firing laser procedure with visual tissue coagulation. Voiding improved after sloughing of necrotic tissue. It is no longer used because better alternatives are available.
Holmium Laser Enucleation of the Prostate (HoLEP)
See endoscopic enucleation of the prostate above and HoLEP.
Transurethral Laser Vaporization of the Prostate
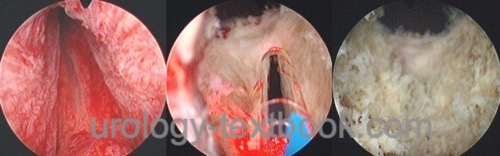
High-power laser application with a KTP-GreenLight or thulium laser vaporizes prostate tissue with good coagulation. This procedure is particularly suitable in patients at increased bleeding risk or receiving anticoagulation. Disadvantages include equipment and fiber costs as well as a higher retreatment risk in large prostates compared with enucleating procedures. For technique and complications, see GreenLight laser vaporization of the prostate.
 |
Results from Randomized Trials
Of the many laser procedures, endoscopic enucleation of the prostate, including HoLEP, and laser vaporization have prevailed. Randomized trials show comparable outcomes and fewer complications than TURP or simple prostatectomy (Kuntz et al., 2004; Kuntz et al., 2008; Reich et al., 2011). In direct comparison of the two laser approaches, HoLEP showed advantages for prostates larger than 60 ml (Elmansy et al., 2012).
Open, Laparoscopic, and Robotic Simple Prostatectomy
 |
 |
Indication
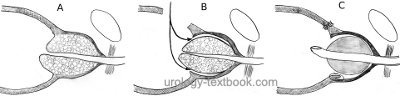
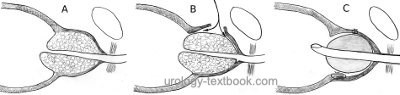
For a very large prostate, simple prostatectomy by an open, laparoscopic, or robot-assisted approach is an option, particularly if sufficient expertise in endoscopic enucleation is unavailable. It is also useful with smaller prostate volumes if resection of a bladder diverticulum or removal of bladder stones is required. Further indications include complex urethral disease, for example after hypospadias repair, or contraindications to the lithotomy position.
Technique and Complications
Transvesical simple prostatectomy according to Harris-Hryntschak is suitable for marked median-lobe enlargement, bladder diverticula requiring surgery, or bladder stones. Retropubic simple prostatectomy according to Millin provides better hemostasis and facilitates apical adenoma dissection, but is less suitable for a large median lobe, bladder disease, or obesity. See transvesical and retropubic simple prostatectomy for details.
New Interventional Treatment Options
Prostatic Artery Embolization (PAE)
Prostatic artery embolization is an interventional radiologic procedure for prostate-volume reduction. It is used for LUTS/BPS and for treatment-refractory prostatic bleeding.
Indication
PAE is an alternative to TURP or simple prostatectomy for voiding symptoms or recurrent gross hematuria without relevant associated pathology, such as bladder stones or large diverticula.
Technique
The prostatic arteries are selectively catheterized and small embolic particles are injected while carefully preserving arteries supplying the rectum, bladder, and penis. Bilateral embolization should be achieved whenever possible. Subsequent ischemia and prostate-volume reduction result in gradual improvement of LUTS.
Results
Improvement of voiding symptoms begins after months and may continue over time. Compared with TURP, PAE is generally less effective with respect to urinary flow, residual urine, and prostate volume, but can achieve clinically relevant symptom improvement with appropriate patient selection (Abt et al., 2018; Ray et al., 2018). PAE has also been used for urinary retention in patients unsuitable for TURP, with success rates of 60–80 %.
Complications
Transient dysuria, pelvic pain, hematospermia, and reduced ejaculatory volume are common. Urinary retention, infection, relevant radiation exposure, nontarget embolization of the bladder, rectum, or penis, and angiographic complications are rare.
Transurethral Microwave Therapy (TUMT)
Technique
Microwave energy thermally damages prostate tissue while the urethral mucosa is cooled. Coagulative necrosis, apoptosis, and denervation can lead to volume reduction and symptom improvement.
Indication
TUMT has largely been replaced by more effective endoscopic, laser-based, and minimally invasive procedures.
Results
Symptom improvement is variable, and objective parameters improve less reliably than after TURP or enucleation. Postoperative urinary retention and retreatment are common.
Transurethral Needle Ablation of the Prostate (TUNA)
Technique
Needle probes are inserted into the adenoma under direct vision; radiofrequency energy induces thermal necrosis of the adenoma. The procedure can be performed under local or spinal anesthesia.
Results
TUNA is now rarely used. Symptom improvement is less pronounced and retreatment is more common than after TURP; postoperative urinary retention may occur.
Transurethral Vaporization of the Prostate (TUVP)
Technique
A specific current application produces two effects: tissue near the electrode is vaporized, whereas tissue farther away is coagulated. Electrodes are shaped as a rolling cylinder or a thick loop.
Results
Randomized trials show comparable results for TUVP and TURP, without clear clinical advantages of TUVP. Blood loss tends to be lower with TUVP.
Transurethral UroLift Procedure
The UroLift procedure is a nonablative minimally invasive technique for relieving obstruction of the prostatic urethra (Berges et al., 2013). It is an option for patients with bothersome LUTS/BPS, a prostate volume below 60 ml, and no significant median lobe. Advantages include low surgical morbidity and complication rates and preservation of antegrade ejaculation.
Technique
Depending on prostate size, 2–6 small tissue retractors are inserted transurethrally with an applicator. They compress prostate tissue and create a channel between the bladder neck and sphincter.
Results
Long-term data show durable symptom improvement with largely preserved erectile and ejaculatory function. Deobstruction is less pronounced than with resecting or enucleating procedures, and retreatment is more frequent (Roehrborn et al., 2017).
Image-Guided Robotic Waterjet Ablation of the Prostate
Transrectal ultrasound identifies the areas of the prostate to be removed. The robotically guided water jet (AquaBeam) removes tissue within minutes; hemostasis is achieved with a traction irrigation catheter or subsequent electrocautery.
Results
Aquablation markedly improves IPSS and urinary flow and is also suitable for larger prostates. Advantages include standardized image-guided resection and comparatively favorable ejaculatory outcomes compared with TURP. Disadvantages are relatively high bleeding risk, cost, device dependence, and lack of histology.
Rezum Water Vapor Ablation of the Prostate
Under local anesthesia, needles are inserted cystoscopically into prostate tissue. Water vapor is delivered through the needles, producing thermal necrosis.
Results
Rezum is well tolerated and preserves sexual function. Deobstruction is less pronounced and slower than after TURP or enucleation; postoperative dysuria, urinary retention, and temporary catheterization are common.
| BPH treatment | Index | Seminal vesicle stones |
Index: 1–9 A B C D E F G H I J K L M N O P Q R S T U V W X Y Z
References
Andriole u.a. 2004 ANDRIOLE, G. L. ;
ROEHRBORN, C. ; SCHULMAN, C. ; SLAWIN, K. M. ;
SOMERVILLE, M. ; RITTMASTER, R. S.:
Effect of dutasteride on the detection of prostate cancer in men with
benign prostatic hyperplasia.
In: Urology
64 (2004), Nr. 3, S. 537–41; discussion 542–3
Burnett und Wein 2006 BURNETT, A. L. ; WEIN,
A. J.:
Benign prostatic hyperplasia in primary care: what you need to know.
In: J Urol
175 (2006), Nr. 3 Pt 2, S. S19–24
Chapple 2004 CHAPPLE, C. R.:
Pharmacological therapy of benign prostatic hyperplasia/lower urinary
tract symptoms: an overview for the practising clinician.
In: BJU Int
94 (2004), Nr. 5, S. 738–44
DGU Guideline, “S2e Leitlinie Diagnostik und Therapie des Benignen Prostatasyndroms (BPS).,” 2023. [Online]. Available: https://register.awmf.org/assets/guidelines/043-034l_S2e_Diagnostik_Therapie_benignes_Prostatasyndrom_2023-04.pdf
Donovan u.a. 2000 DONOVAN, J. L. ; PETERS,
T. J. ; NEAL, D. E. ; BROOKES, S. T. ; GUJRAL,
S. ; CHACKO, K. N. ; WRIGHT, M. ; KENNEDY, L. G. ;
ABRAMS, P.:
A randomized trial comparing transurethral resection of the prostate,
laser therapy and conservative treatment of men with symptoms associated with
benign prostatic enlargement: The CLasP study.
In: J Urol
164 (2000), Nr. 1, S. 65–70
“EAU Guideline: Non-neurogenic Male LUTS,” Available: https://uroweb.org/guidelines/treatment-of-non-neurogenic-male-luts/.
Kopp, R. P.; Freedland, S. J. & Parsons, J. K.
Associations
of benign prostatic hyperplasia with prostate cancer: the debate continues.
Eur
Urol, 2011, 60, 699-700; discussion 701-2.
Ørsted, D. D.; Bojesen, S. E.; Nielsen, S. F. &
Nordestgaard, B. G.
Association of clinical benign prostate hyperplasia
with prostate cancer incidence and mortality revisited: a nationwide
cohort study of 3,009,258 men.
Eur Urol, 2011, 60,
691-698.
Parsons, J. Kellogg; Messer, Karen; White, Martha;
Barrett-Connor, Elizabeth; Bauer, Douglas C; Marshall, Lynn M; in Men
(MrOS) Research Group, Osteoporotic Fractures & the Urologic Diseases in
America Project
Obesity increases and physical activity decreases lower
urinary tract symptom risk in older men: the Osteoporotic Fractures in Men
study.
Eur Urol, 2011, 60, 1173-1180.
Reich u.a. 2006 REICH, O. ; GRATZKE, C. ;
STIEF, C. G.:
Techniques and long-term results of surgical procedures for BPH.
In: Eur Urol
49 (2006), Nr. 6, S. 970–8; discussion 978
Uygur u.a. 1998 UYGUR, M. C. ; GUR, E. ;
ARIK, A. I. ; ALTUG, U. ; EROL, D.:
Erectile dysfunction following treatments of benign prostatic
hyperplasia: a prospective study.
In: Andrologia
30 (1998), Nr. 1, S. 5–10
 Deutsche Version: Operative Therapie der benignen Prostatahyperplasie
Urology-Textbook.com – Choose the Ad-Free, Professional Resource
This website is designed for physicians and medical professionals. It presents diseases of the genital organs through detailed text and images. Some content may not be suitable for children or sensitive readers. Many illustrations are available exclusively to Steady members. Are you a physician and interested in supporting this project? Join Steady to unlock full access to all images and enjoy an ad-free experience. Try it free for 7 days—no obligation.
New release: The first edition of the Urology Textbook as an e-book—ideal for offline reading and quick reference. With over 1300 pages and hundreds of illustrations, it’s the perfect companion for residents and medical students. After your 7-day trial has ended, you will receive a download link for your exclusive e-book.